


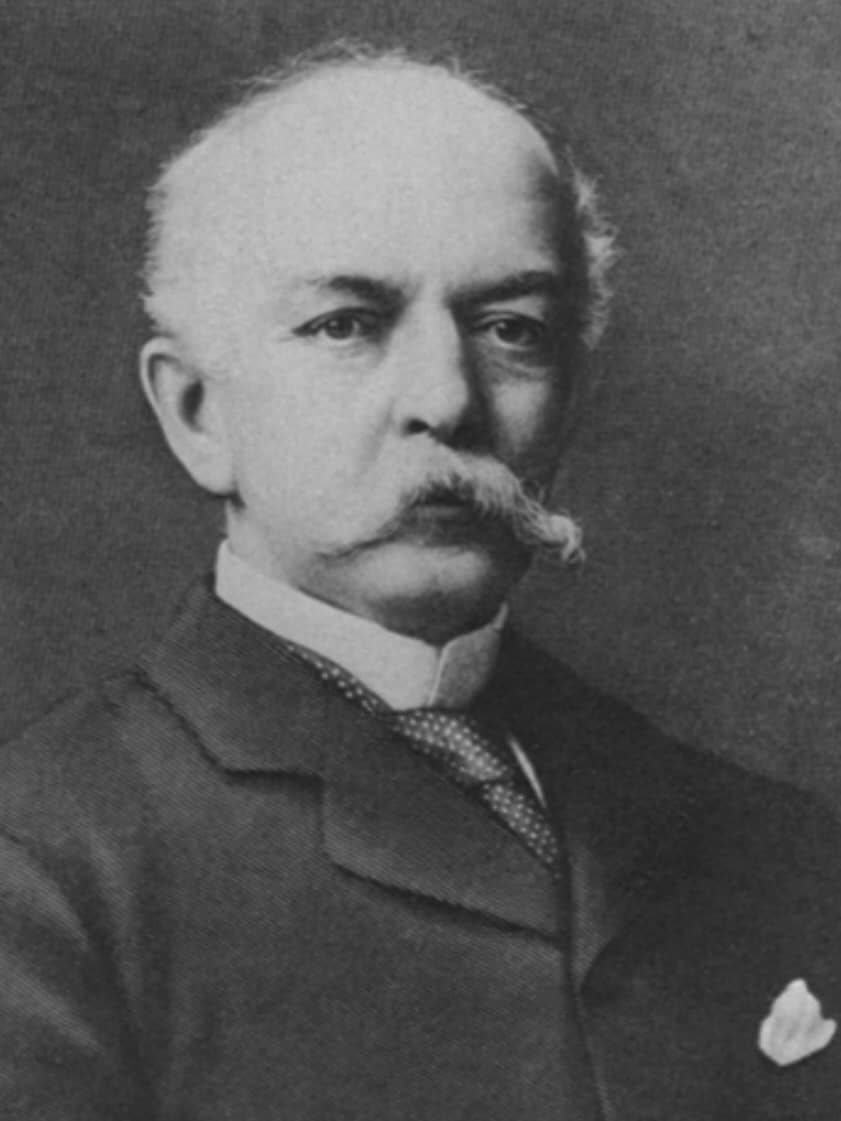
Charles Heber McBurney (1845-1913) was an American general surgeon.
McBurney advocated early surgical intervention for appendicitis and is eponymously associated with the McBurney point (1889), a clinical site of maximal abdominal tenderness, and the McBurney incision (1894), a muscle-splitting operative approach to appendicectomy.
Beyond appendicitis, McBurney contributed to the operative management of pyloric stenosis, fracture-dislocations of the shoulder, haemorrhage control during hip disarticulation and transduodenal extraction of common bile duct stones. He also advocated the adoption of sterilised rubber gloves to improve operative asepsis.
Biography
- Born on February 17, 1845, in Roxbury, Massachusetts. Educated at Roxbury Latin School and a private school in Boston.
- 1862 – Entered Harvard University.
- 1866 – Graduated from Harvard with an AB and later received an AM.
- 1870 – Graduated MD from the College of Physicians and Surgeons in New York.
- 1870–1872 – Undertook 18 months of postgraduate clinical training at Bellevue Hospital, followed by further study at major European medical centres including Vienna, Paris and London.
- 1872–1873 – Returned to New York and commenced medical and surgical practice. Joined the College of Physicians and Surgeons as a demonstrator in anatomy.
- 1880 – Appointed assistant surgeon at Bellevue Hospital.
- 1888 – Appointed surgeon-in-chief at Roosevelt Hospital, New York, the institution with which much of his subsequent surgical work became associated.
- 1889 – Appointed Professor of Surgery at the College of Physicians and Surgeons. On November 13, presented Experience with Early Operative Interference in Cases of Disease of the Vermiform Appendix before the New York Surgical Society. McBurney identified the localised site of greatest tenderness subsequently known as McBurney point.
- 1892 – The William J. Syms Operating Pavilion opened at Roosevelt Hospital. McBurney had planned and directed construction of the purpose-built surgical facility, which became an important centre for surgical teaching and operative research.
- 1894 – Became Professor of Clinical Surgery at the College of Physicians and Surgeons. Published The incision made in the abdominal wall in cases of appendicitis, with a description of a new method of operating, describing a muscle-splitting approach subsequently known as the McBurney incision.
- 1896 – Published further work on the operative management of fracture-dislocation of the humerus and injuries of the distal femoral epiphysis.
- 1901 – One of the surgeons called to Buffalo following the shooting of US President William McKinley. McBurney participated in the subsequent surgical consultation and publicly reported apparent improvement in the President’s condition before McKinley’s later deterioration and death.
- 1905 – Retired from active surgical work because of declining health.
- 1907 – Became Professor Emeritus of Surgery at the College of Physicians and Surgeons.
- Died on November 7, 1913 in Brookline, Massachusetts, aged 68
Medical Eponyms
McBurney point (1889)
In 1889, McBurney described a site of maximal tenderness elicited by pressure with one finger in patients with acute appendicitis. He located this point approximately 1½–2 inches from the right anterior superior iliac spine along a line towards the umbilicus.
The seat of greatest pain, determined by the pressure of one finger, has been very exactly between an inch and a half and two inches from the anterior spinous process of the ilium on a straight line drawn from that process to the umbilicus
McBurney 1889
Lewis Atterbury Stimson introduced the designation McBurney’s point in 1890. Subsequent descriptions increasingly treated the clinical finding as a fixed anatomical landmark, often placing it one-third of the distance from the anterior superior iliac spine towards the umbilicus. This differs from McBurney’s original description.
The anatomical evolution and diagnostic significance of the landmark are examined in the dedicated McBurney point article.
McBurney Incision (1894)
In July 1894, McBurney published a new muscle-splitting approach to appendicectomy, first documented in an operation performed on December 18, 1893. Unlike his earlier oblique incision, which divided the deeper abdominal muscles transversely, the new technique separated the fibres of the external oblique, internal oblique and transversus abdominis along their natural directions.
The incision is an oblique one about four inches long. It crosses a line drawn from the anterior iliac spine to the umbilicus nearly at right angles about one inch from the iliac spine, and is so situated that its upper third lies above that line
McBurney 1894
McBurney argued that preserving the crossed arrangement of the abdominal wall musculature would minimise haemorrhage, postoperative pain and incisional hernia. The technique subsequently became known as the McBurney incision, or gridiron incision, and became an established approach to open appendicectomy.
The historical priority of the operation remains disputed. Louis L. McArthur described a comparable technique in November 1894, claiming earlier operative use. McBurney holds publication priority, although the evidence does not establish who first developed the approach.
Key Medical Contributions
McBurney made significant contributions to orthopaedic trauma, haemorrhage control, operative asepsis and biliary surgery.
Operative treatment of pyloric stenosis (1885–1886)
1885 – On December 22, McBurney presented Two Cases of Operation for Pyloric Stenosis before the New York Surgical Society, describing two attempts to relieve benign gastric outlet obstruction using digital dilatation of the pylorus, a procedure introduced by Pietro Loreta in 1882.
Both operations, performed on July 6, 1885, were unsuccessful. The first patient died from haemorrhage associated with a tear of the pyloric mucosa, while the second died following postoperative suppression of urine. McBurney used the cases to examine the risks of forcible pyloric dilatation and the different anatomical mechanisms underlying gastric outlet obstruction.
Great example of McBurney’s critical evaluation of emerging surgical techniques and his willingness to report adverse outcomes.
Fracture-dislocation of the shoulder (1894–1896)
1894 – On January 10, McBurney presented Dislocation of the Humerus Complicated by Fracture at or near the Surgical Neck, with a New Method of Reduction before the New York Surgical Society. Working with Charles N. Dowd, he reviewed 117 previously reported cases of this uncommon and difficult injury.
McBurney described a new operative method to overcome the difficulty of manipulating a displaced humeral head separated from the shaft by fracture. Through a surgical incision, a hole was drilled into the proximal fragment and a specially designed right-angled steel hook inserted to apply controlled traction and achieve reduction. He reported successful reduction with restoration of limb function.
1896 – On January 22, McBurney presented The Reduction of Dislocation of the Humerus complicated by Fracture at the Anatomical Neck. He demonstrated that his earlier technique could also be applied to fracture-dislocations involving the anatomical neck, where the small proximal fragment made conventional reduction particularly difficult.
Control of haemorrhage during hip disarticulation (1897)
1897 – On February 24, McBurney presented Direct Intra-Abdominal Finger-Compression of the Common Iliac Artery during Amputation at the Hip-Joint before the New York Surgical Society. He described a method of controlling haemorrhage during hip disarticulation by introducing an assistant’s finger through a small abdominal incision to compress the common iliac artery directly.
The approach provided proximal vascular control without tourniquets or other appliances obstructing the operative field. McBurney reported three successful cases, including a patient with femoral sarcoma, one with extensive tuberculosis of the femur and a child with severe traumatic injury.
Rubber gloves and operative asepsis (1898)
1898 – On March 9, McBurney presented The Use of Rubber Gloves in Operative Surgery before the New York Surgical Society. He argued that contamination from the hands of surgeons and assistants remained an important potential source of postoperative wound infection despite increasingly sophisticated antiseptic practices.
Rubber surgical gloves had already been introduced by William Stewart Halsted and colleagues at Johns Hopkins. McBurney advocated the use of sterilised India-rubber gloves as a reliable barrier between the operating team’s hands and the surgical wound. Unlike human skin, rubber gloves could be sterilised by boiling and their sterility experimentally demonstrated.
Biliary surgery and transduodenal extraction of common duct stones (1898)
1892 – McBurney developed a transduodenal approach for removing impacted calculi from the distal common bile duct. Rather than incising the common bile duct externally, he opened the descending duodenum, identified the ampullary orifice and enlarged it sufficiently to deliver the stone into the intestinal lumen.
1898 – On May 11, McBurney presented Removal of biliary calculi from the common duct by the duodenal route before the New York Surgical Society. He described the successful treatment of a 44-year-old woman with prolonged obstructive jaundice. At operation, a calculus impacted near the ampulla was removed through a duodenal incision, followed by closure of the duodenal wall.
He described this approach as ‘quicker, cleaner and safer, in my opinion, than the operation which is usually done’
McBurney and the McKinley Assassination (1901)
On September 6, 1901, US President William McKinley was shot twice at close range by Leon Czolgosz while attending the Pan-American Exposition in Buffalo, New York. One bullet caused a superficial wound over the sternum. The second entered the abdomen, perforating the anterior and posterior walls of the stomach before passing into the retroperitoneum.
McKinley underwent emergency laparotomy at the Exposition hospital. The operation was led by Buffalo surgeon and gynaecologist Matthew D. Mann, assisted by Herman Mynter and others. The gastric wounds were sutured, but the bullet could not be located and was left in situ.
McBurney was not present for the initial operation. As one of America’s best-known surgeons, he was subsequently summoned to Buffalo for consultation and arrived at the Milburn residence, where McKinley was being cared for, on September 9.
The President initially appeared to recover. McBurney publicly supported the treatment undertaken by the Buffalo surgeons and emphasised the importance of the rapid decision to operate. As McKinley’s apparent improvement continued, McBurney became increasingly optimistic about his prognosis.
On September 10, McBurney considered the immediate danger from peritonitis to have largely passed. Contemporary reports record him as sufficiently confident in McKinley’s recovery that he saw no indication to use X-rays merely to locate the retained bullet.
However, McKinley’s condition deteriorated abruptly on September 12–13 with tachycardia, weakness and progressive cardiovascular collapse. He died at 02:15 on September 14, 1901, eight days after the shooting.
Post-mortem examination demonstrated that both sutured gastric perforations remained closed and there was no generalised peritonitis. However, gangrenous tissue surrounded the gastric wounds and extended along the track of the bullet into the retroperitoneum, involving the upper pole of the kidney and pancreas. The bullet itself was never recovered.
McBurney was subsequently one of the physicians named in the official report of the case. The episode provides an illustration of the limitations of contemporary postoperative assessment. Successful closure of the visceral injuries with apparent clinical recovery concealed progressive tissue necrosis for which there was, in the pre-antibiotic era, little effective treatment.
In response to the controversy, the attending physicians issued a joint statement asserting that:
We say again that there was never a serious disagreement among the professional attendants as to any of the symptoms or as to treatment of the case or as to the bulletins which were issued. A very unusual harmony of opinion and of action prevailed all through the case. The unfortunate result could not have been foreseen before the unfavorable symptoms declared themselves late on the sixth day, and could not have been prevented by any human agency.
Major Publications
- McBurney C. Two Cases of Operation for Pyloric Stenosis. Annals of Surgery. 1886; 3(5): 372–380.
- McBurney C. Experience with early operative interference in cases of disease of the vermiform appendix. New York Medical Journal, 1889; 50: 676-684.
- McBurney C. The Indications for Early Laparotomy in Appendicitis. Annals of Surgery. 1891; 13(4): 233–254.
- McBurney C. II. Dislocation of the Humerus Complicated by Fracture at or near the Surgical Neck, with a New Method of Reduction. Ann Surg. 1894 Apr;19(4):399-415.
- McBurney C. The incision made in the abdominal wall in cases of appendicitis, with a description of a new method of operating. Annals of Surgery 1894: 20: 38–43
- McBurney C. I. The Reduction of Dislocation of the Humerus complicated by Fracture at the Anatomical Neck; Operative Treatment of Separation of the Lower Epiphysis of the Femur. Ann Surg. 1896 May;23(5):501-9.
- McBurney C. V. Direct Intra-Abdominal Finger-Compression of the Common Iliac Artery during Amputation at the Hip-Joint. Ann Surg. 1897 May;25(5):610-3.
- McBurney C. IV. The Use of Rubber Gloves in Operative Surgery. Ann Surg. 1898 Jul;28(1):108-19.
- McBurney C. Removal of biliary calculi from the common duct by the duodenal route. Annals of Surgery 1898; 28: 481–486
References
Biography
- JAMA Review: Charles McBurney (1845–1913)—point, sign, and incision. JAMA 1966; 197: 1098–1099
- Yale SH, Musana KA. Charles Heber McBurney (1845 – 1913). Clin Med Res. 2005; 3(3): 187–189.
- Bibliography. McBurney, Charles 1845-1913. WorldCat Identities
Eponymous terms
- McArthur LL. Choice of incisions of abdominal wall; especially for appendicitis. Chicago medical recorder 1894; 7(1): 289-292.
- Morgenstern L. Charles McBurney (1845-1913). Afield from the appendix. Surg Endosc. 1996 Apr;10(4):385-6
- Soda K et al. Detection of pinpoint tenderness on the appendix under ultrasonography is useful to confirm acute appendicitis. Arch Surg. 2001; 136(10): 1136-1140.
- Andersson RE. Meta-analysis of the clinical and laboratory diagnosis of appendicitis. Br J Surg 2004; 91(1): 28-37
- Grover CA, Sternbach G. Charles McBurney: McBurney’s point. The Journal of emergency medicine. 2012; 42 (5): 578-81.
- Thiery, M. Charles McBurney (1845–1913) and McBurney’s point. Gynecological Surgery, 2009; 6(4): 411–413
- Cadogan M. Appendicitis eponymous signs. LITFL
Eponym
the person behind the name

BA MA (Oxon) MBChB (Edin) FACEM FFSEM. Emergency physician, Sir Charles Gairdner Hospital. Passion for rugby, medical history, medical education, and asynchronous learning #FOAMed evangelist. Editor-in-Chief and Webmaster of Life in the Fast lane, LITFL | On Call 4e| Eponyms | Books | Horology |