



Henry Harrington Janeway (1873-1921) was an American physician and pioneer for radiation therapy in the treatment of cancer.
Janeway was the first to design a laryngoscope specifically for anaesthesia and introduced the novel feature of a battery powered laryngoscope. His interest in anaesthesia extended to mechanical ventilation where his experiments in dogs with colleague Dr Nathan Green, lead to the development of the ‘rhythmic inflation apparatus’ – an intermittent positive pressure ventilator. Whilst it never entered clinical practice, it was a forerunner for modern ventilators that followed.
Janeway and Green also collaborated to develop the ‘Green button’ a technique for gastric anastomosis after resection of cardial gastric carcinoma. His work in gastroenterology saw him introduce the Janeway gastrostomy procedure, a technique which stands the test of time and is still used in palliative care medicine today.
Janeway is most credited for his pioneer work in radiation therapy and was the first to advance the use of radium as a first line therapeutic agent in cervical carcinoma. His technique for burying radium emanation into the cervix, the use of dental modelling compound to enhance the application of radium and the use of radium emanation needles, all originated from his clinic.
Biography
- Born on March 19, 1873 in New Brunswick, New Jersey
- 1889 – Graduates from Rutgers College
- 1898 – MD, College of Physicians and Surgeons
- 1898-1900 Internship at Roosevelt Hospital
- 1906 – Commences work in the experimental laboratories of his medical school and specialises in surgery and dermatology
- 1907 – Dermatological practice with his father-in-law Dr Bulkley for the next two years and publishes several articles about skin and cancer pathology
- 1909 – Chief of the Laboratory for Experimental Research of Physicians and Surgeons and conducts work in gastric and oesophageal surgery, blood pressure and shock; collaborates with Dr Nathan W Green and develops the ‘Green button’ for surgical anastomosis of the oesophagus and stomach; published in JAMA with step-by-step guide ‘Experimental intrathoracic esophageal surgery’
- 1910 – Collaborates again with Green in experimenting with mechanical ventilation during thoracic surgery on animals; publishes findings in Annals of Surgery as “Artificial respiration and intrathoracic oesophageal surgery.’; devises an apparatus coined ‘rhythmic inflation apparatus’ to deliver positive pressure ventilation.
- 1913 – Publishes article on Intra‐tracheal anesthesia from the standpoint of the nose, throat and oral surgeon with a description of a new instrument for catheterizing the trachea and devises a new laryngoscope to include a battery powered light source, the first of its kind.
- Proposes a novel method for gastrostomy, described in his paper on ‘The relation of gastrostomy to inoperable carcinoma of the esophagus: with a description of a new method of performing gastrostomy’ – and so the term ‘Janeway Gastrostomy’ is coined
- 1914 – Attending Surgeon and Chief of the Radium Department at Memorial Hospital in New York where he develops and advances the use of radium as a therapeutic agent in cancer; Janeway is the first to advocate for radium use in the treatment of cervical cancer by ‘burying radium emanation’ in the cervix.
- 1917 – Publishes multiple articles on Radium therapy in cancer including his landmark article on ‘The Treatment of Uterine Carcinoma’
- Dies on February 1, 1921, aged 47 from cancer
Medical Eponyms and Key Medical Contributions
Janeway Laryngoscope (1913)
In 1913, Janeway published Intra‐tracheal anesthesia from the standpoint of the nose, throat and oral surgeon with a description of a new instrument for catheterizing the trachea. He introduced the novel design of a battery powered laryngoscope, the first of its kind specifically designed for anaesthesia. Initial designs were complex and included a telescopic prism with eye piece to visualise the catheter and larynx. A central notch kept the catheter midline during placement
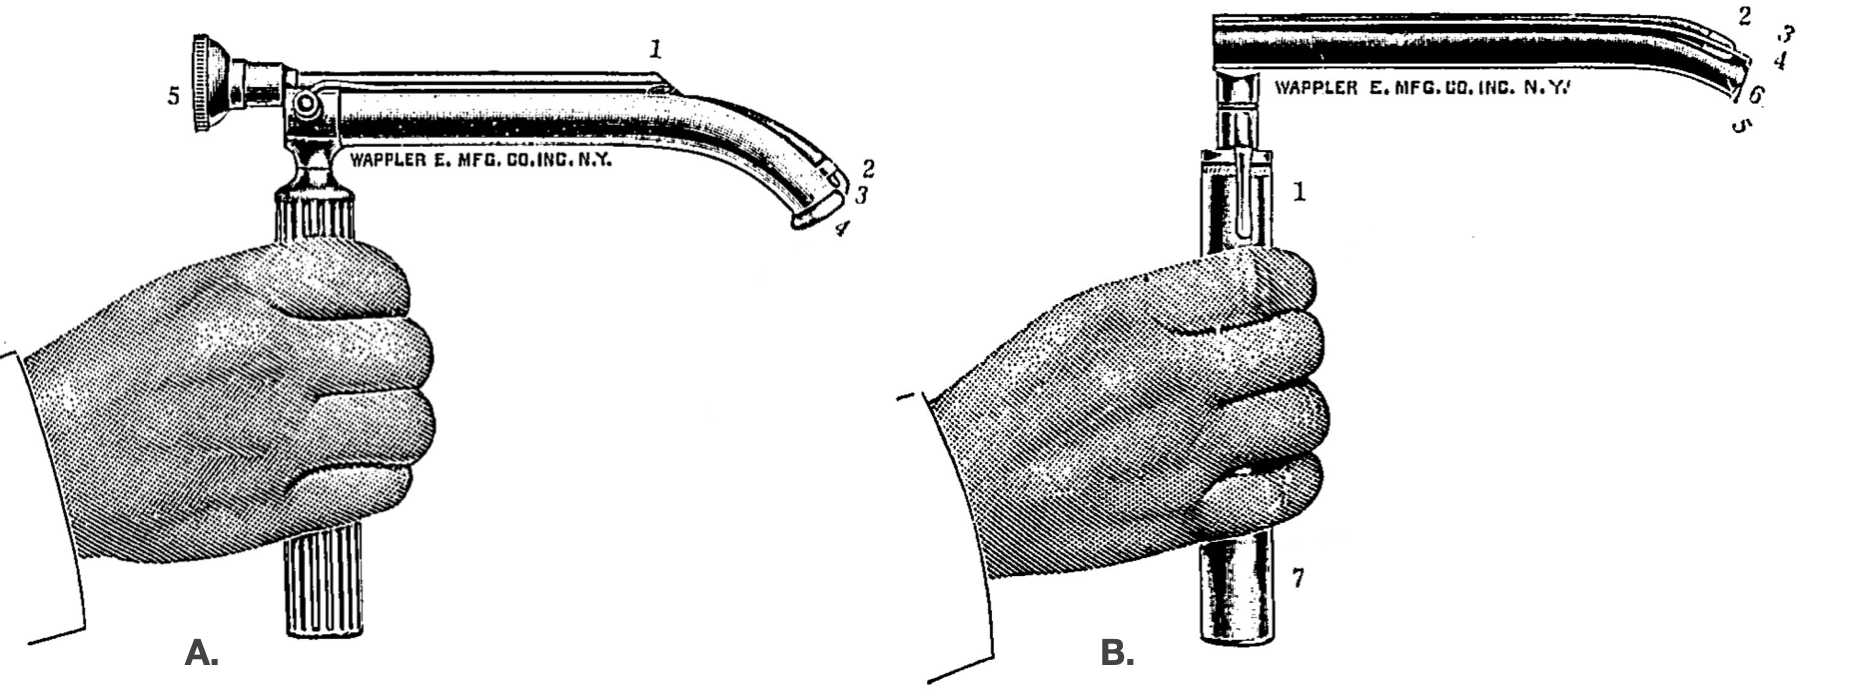
In the same paper, Janeway then described a simpler direct-vision instrument with a distal light source with the battery incorporated within the handle of the laryngoscope itself and a blade that was shortened and curved at its distal end to facilitate delivery of the catheter through the vocal cords. Because catheter placement could now occur under direct vision, it obliviated the need for the complex prism mechanism.
Of his invention, he remarks:
…offers a very great advantage. It permits of easy catheterization of the larynx even when the patients’ pharyngeal reflexes are not completely abolished and without the necessity for the same degree of extension of the head. The omission of the telescope greatly simplifies the instrument
Laryngoscope. 1913
Whilst Janeway experienced much success with his invention in head and neck and thoracic procedures, his laryngoscope never gained widespread popularity
Gastric surgery
The risk of infection when the oesophagus was opened operatively was a well recognised issue at the time. Janeway’s experimental work in thoracic surgery in animals was met with disaster
Not one case of carcinoma of the cardia operated upon the transthoracic route has been reported that has lived more than five days…in looking over the results of this last winter’s work…we have operated upon over 50 animals…the animals die with pus in the chest, with collapsed lungs, often with a general infection, or with exhaustion from labored breathing…
Where and from what does the infection come? To a certain extent by direct contamination from the opened viscera”
New York Surgical Society. 1911
His collaboration with Dr Nathan Green resulted in the development of the ‘Green button’ which allowed anastomosis between the oesophagus and stomach without freely opening either organ.
By the pressing together of the opposing halves of the button through the approximated and unopened walls of the oesophagus and stomach a union of these viscera is effected without the slightest contamination of the field of operation, and more rapidly than it can be done by any other method
Green NW, Janeway HH, Ann Surg 1910
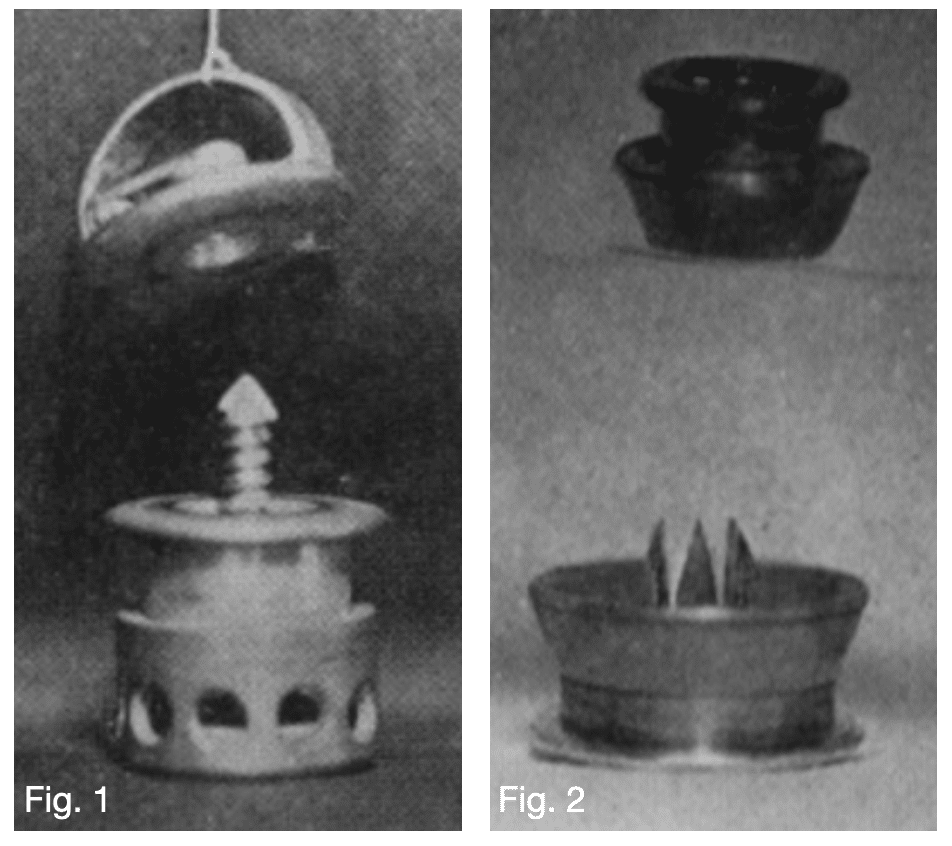
Fig 2: Button for end-to-side anastomosis.
Green NW, Janeway HH, Ann Surg 1910
Janeway Gastrostomy (1913)
In 1913, Henry Harrington Janeway described a technique for creating a permanent gastrostomy using a flap of anterior gastric wall. The flap was fashioned into a mucosa-lined canal and brought to the skin to form a stoma, allowing intermittent insertion of a small-bore tube for feeding or medication without requiring a permanent indwelling catheter.
However, Janeway was not the first to describe this approach. In 1901, Belgian surgeon Antoine Dépage (1862–1925) had published Nouveau procédé pour la gastrostomie using a tubularised flap of gastric wall. Janeway acknowledged the earlier operation in his original publication, noting that he had developed his own technique independently:
The fistula has worked so well in dogs, not leaking even during vomiting or barking, that I have used the same technic with equal success on five human beings during the past year. The operation is similar to De Page’s gastrostomy, with which I was unfamiliar at the time of the experimental development of my own procedure. Whether the operation to be described be viewed as merely a modification of De Page’s method or as sufficiently different to warrant its being designated as a new procedure, matters little.
Janeway HH, JAMA. 1913
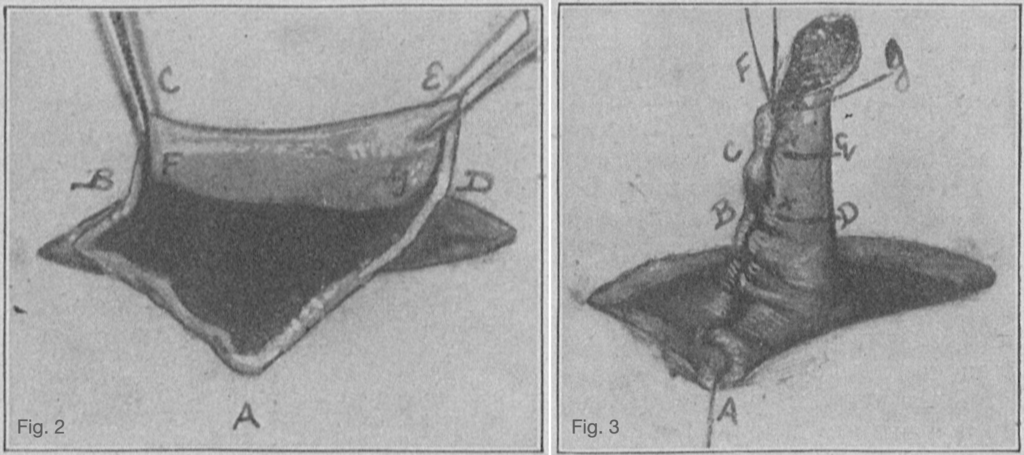
Fig 3: New canal, tubular in shape, formed by after-suture of plastic procedure shown in Fig 2.
Janeway HH, JAMA. 1913
The procedure subsequently became known as the Janeway gastrostomy, or Dépage–Janeway gastrostomy. Although percutaneous endoscopic gastrostomy (PEG) is now generally preferred, the technique remains an option for selected patients requiring long-term enteral access when PEG is unsuitable.
Radiation therapy
Radiotherapy developed rapidly following the discovery of X-rays by Wilhelm Röntgen in 1895 and radium by Marie and Pierre Curie in 1898. In 1903, Willian B. Colley used radiation therapy to treat 84 patients with tongue cancer. Despite poor results X-rays and radium continued to be investigated for the treatment of malignant disease.
Janeway was instrumental in advancing radium therapy at Memorial Hospital, New York, where he became Chief of the Radium Department in 1914. He advocated radium as an important treatment for cervical carcinoma and other localised malignancies, helping establish more precise methods of intracavitary, interstitial and surface application. His 1917 report, Radium therapy in cancer at the Memorial Hospital, and The Treatment of Uterine Carcinoma by Radium (1919) were important contributions to the emerging specialty.
Janeway developed a technique of burying radium emanation in the cervix. He used dental modelling compound to improve radium delivery to the carcinoma site. A mould of the tumour is taken and the lesion of interest is marked on the mould with ink. Grooves are then made with a hot tool and radium tubes placed within these grooves which are then filled with paraffin. This method ensured that radiation is delivered to the target area and remained in position throughout the duration of treatment.
The characteristic of the result among cases cured by radium coupled with the ease by which this result can be obtained far surpasses the results of surgical ablation
Am J Roentgenology. 1918
Of historical significance
Janeway developed a lump on his jaw shortly after graduating medical school. It was proved to be cancerous and Janeway underwent multiple surgeries throughout his life in attempt to cure the cancer that would eventually take his life.
The dissatisfaction with the then current methods for treatment, lead him to pursue his research into radium as a therapeutic agent. It is of great misfortune, that his successes as a physician could not be used to save his own life, however if not for this twist of fate, the many patients who followed may not have benefited from his work.
Janeway Medal and Janeway Lecture
Since 1933, the American Radium Society has sponsored an annual lecture in memory of Janeway and his pioneering work in the therapeutic use of radium.
Lecturers are chosen on the basis of their outstanding scientific contributions. Each lecturer is presented the handsome Janeway Medal. The Medal was originally a large bronze medal, but was changed to a gold medal in 1971.
The first ever Janeway Memorial Lecture was given by his friend Dr James Ewing entitled: Early experience in Radiation therapy [American journal of roentgenology, 1934; 31: 153-190]
Mechanical ventilation
Green and Janeway rhythmic inflation apparatus (1910)
The ability to maintain adequate respiration during thoracic procedures on the open chest was a surgical conundrum during that time. Janeway and Green conducted myriad animal experiments in an effort to circumnavigate this problem.
During their experiments, it was observed that thoracic surgery was more successful when performed under mechanical ventilation
…in working with the intralaryngeal cannula it was noticed that the alternating increase and decrease in intratracheal pressure produced an artificial apnoea which largely eliminated the movements of the diaphragm. The advantages of such an elimination of movement during operation were so apparent that it induced the other of use…to devise another cabinet provided with a mechanism with accomplished during operation a similar cessation of respiratory movements
Green and Janeway. Ann Surg 1910
This lead Janeway and Green to devise a ventilator based on Brauer’s invention for application of intermittent positive pressure ventilation.
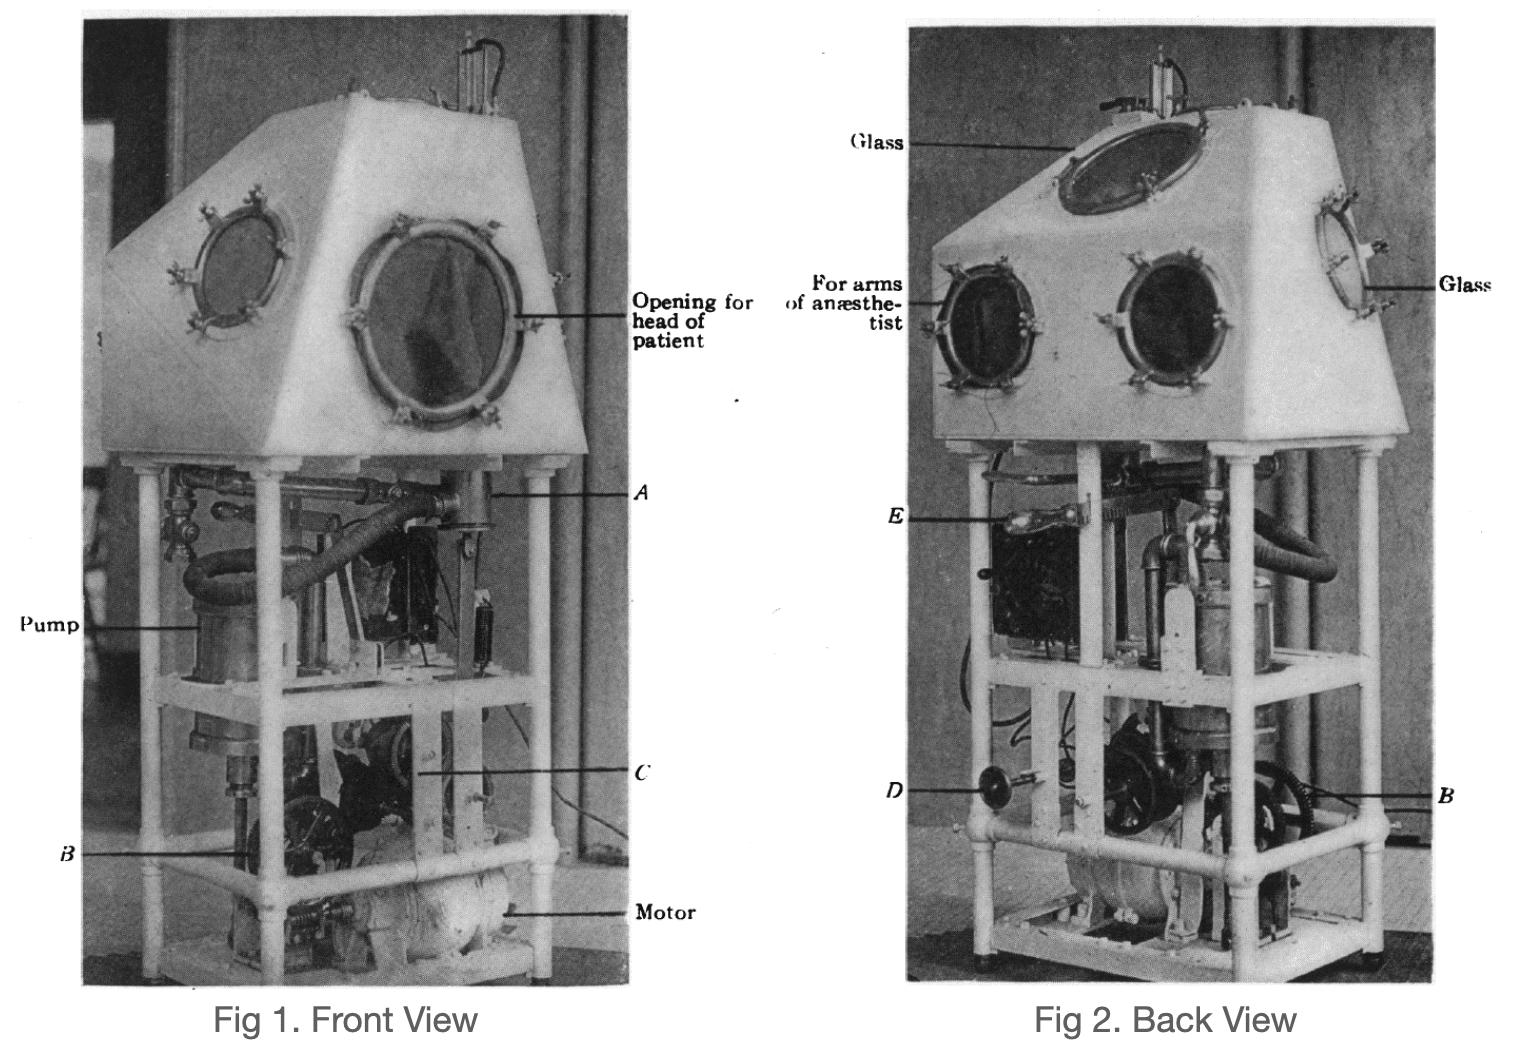
The apparatus consisted of a box with an opening for the patients’ head and for the anaesthetists’ arms to access the patient ‘in case of vomiting or the necessity of cleaning out the pharynx or passing an instrument into the oesophagus or stomach‘
A pump and motor were positioned under the box and a valve (A) controlled by gears (B) and a cone shaped cam (C) allowed intermittent pressure ventilation to be delivered within the cabinet. Respiration rate and inspiratory-expiratory ratio could be adjusted by the anaesthetist by use of a lever (D and E respectively)
Respiration may be uninterruptedly continued with use of such an apparatus….by this apparatus we have kept a fully curarized dog alive for four hours
Green and Janeway. Ann Surg 1910
It was also remarked that because of ‘cerebral anaemia’ induced by the positive pressure surrounding the patients’ head, a lesser amount of ether was required to induce anaesthesia.
While the ‘rhythmic inflation’ apparatus of Janeway and Green was successful in experimental conditions, it never found a place in clinical practice.
Major Publications
- Green NW, Janeway HH. Experimental intrathoracic esophageal surgery. JAMA. 1909; LIII(24): 1975-1978 [Green button]
- Green NW, Janeway HH. VI. Artificial Respiration and Intrathoracic Oesophageal Surgery. Ann Surg. 1910; 52(1): 58-66.
- Janeway HH, Green NW. VII. Cancer of the OEsophagus and Cardia: A Description of an Operation for its Removal by the Transthoracic Route Under Conditions of Differential Pressure. Ann Surg. 1910; 52(1): 67-82
- Green NW, Janeway HH. IX. An Experimental Study of the Management of Post-Operative Thoracic Infections: A Preliminary Report. Ann Surg. 1911; 54(4): 549-53
- Janeway HH, Green NW. Esophagoscopy and gastroscopy. Surgery, Gynecology & Obstetrics. 1911; 13(3): 245-253
- Janeway HH. IX. An Apparatus for Intratracheal Insufflation. Ann Surg. 1912; 56(2): 328-30.
- Janeway HH. Intra‐tracheal anesthesia from the standpoint of the nose, throat and oral surgeon with a description of a new instrument for catheterizing the trachea. The Laryngoscope. 1913; 23(11): 1082-1090 [Janeway Laryngoscope]
- Janeway HH. The relation of gastrostomy to inoperable carcinoma of the esophagus: with a description of a new method of performing gastrostomy. JAMA. 1913; 61(2): 93-95 [Janeway gastrostomy]
- Janeway HH. Results of radium in cancer. JAMA. 1914; LXII(22): 1707-1709
- Janeway HH. XIV. Simple and Complete Forms of Apparatus for Intratracheal Anaesthesia. Ann Surg. 1914; 59(4): 628-30
- Janeway HH. The Nervous System; The Special Senses; The Circulation; Digestion; Hygiene;
- The kidney and bladder; The ductless glands. Lecture notes on physiology. 1915
- Janeway HH. Radium therapy in cancer at the Memorial Hospital, New York (First report: 1915-1916). New York, P. B. Hoeber, inc 1917
- Janeway HH. Cancer of the mucous membranes treated with radium alone. The American Journal of Roentgenology. 1918; 5: 414-421.
- Janeway HH. The treatment of tumors of the superior maxilla. Ann Surg. 1918; 68(4): 353-70
- Janeway HH. The Treatment of Cancer of the Lip by Radium: A Report of Twenty-four Cases. Journal of the American Medical Association, 1918; 70(15): 1051-1058.
- Janeway HH. The Treatment of Uterine Carcinoma by Radium. Surgery, Gynecology & Obstetrics. 1919; 29: 242-265
- Janeway HH. The treatment of malignant tumors of the thymus gland by radium. Ann Surg. 1920 Apr;71(4):460-71
- Janeway HH. Treatment of cancer, particularly of the tongue, tonsil and rectum, by buried emanation,
- The American Journal of Roentgenology. 1920; 7: 92-101
- Janeway HH. Radium therapy in cancer at the Memorial Hospital, New York (Second report). New York, P. B. Hoeber, inc 1923
References
Biography
- Obituary. Dr Henry H. Janeway. Radium. 1921; 16(6): 81-82
- Henry Harrington Janeway. In: 50th Anniversary Book, The American Association for Thoracic Surgery (AATS)
- Bibliography. Janeway, Henry Harrington 1873-1921. WorldCat Identities
Eponymous terms
- Depage A. Nouveau procédé pour la gastrostomie (A new method of gastrostomy). Journal de chirurgie et annales de la Société belge de chirurgie. 1901; 1: 715–718.
- Edling L. On Plastic Means of Application in Radium Therapy, Acta Radiologica, 1921;1(1):60-88
- Fletcher GH. Cancer of the uterine cervix. Janeway lecture, 1970. Am J Roentgenol Radium Ther Nucl Med. 1971 Feb;111(2):225-42.
- Minard G. The history of surgically placed feeding tubes. Nutr Clin Pract. 2006 Dec;21(6):626-33.
Eponym
the person behind the name

FACEM. Emergency physician and researcher at Sir Charles Gairdner Hospital, Perth

BA MA (Oxon) MBChB (Edin) FACEM FFSEM. Emergency physician, Sir Charles Gairdner Hospital. Passion for rugby, medical history, medical education, and asynchronous learning #FOAMed evangelist. Editor-in-Chief and Webmaster of Life in the Fast lane, LITFL | On Call 4e| Eponyms | Books | Horology |