


Rovsing sign
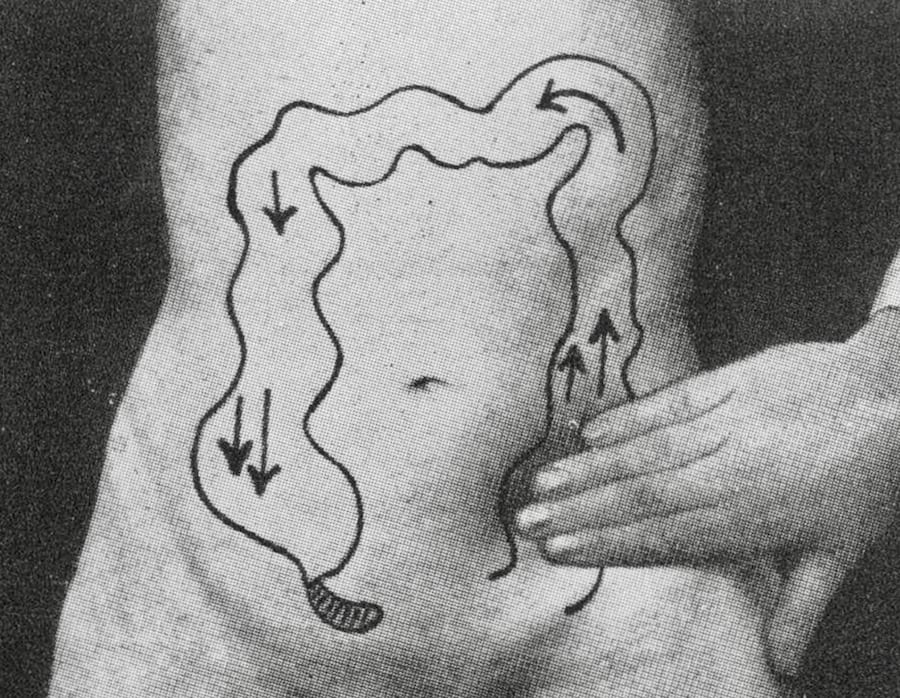
Rovsing sign (original) is the reproduction of pain at McBurney’s point by compression of the descending colon while maintaining pressure and moving the hands proximally towards the left colonic flexure. Rovsing proposed that this manoeuvre forced colonic contents and gas retrogradely towards the caecum, increasing pressure and producing pain from an inflamed appendix or caecum.
The manoeuvre commonly taught today as Rovsing sign involves right lower quadrant pain produced by palpation or continued pressure applied to the left lower quadrant. This is not the technique originally described by Rovsing in 1907. It more closely resembles the indirect pressure sign described by Emil Perman in 1904.
For clarity, the two manoeuvres can be distinguished as:
- Perman sign / modern “Rovsing sign”: pressure on the left side of the abdomen produces pain localised to the right iliac fossa or ileocaecal region.
- Rovsing sign (original): the descending colon is compressed between the hands and, while maintaining compression, the hands are moved proximally towards the left colonic flexure, reproducing pain at McBurney’s point.
The term Perman–Rovsing sign has been used for indirect right-sided pain elicited by left-sided abdominal pressure. However, the historical descriptions suggest that Perman and Rovsing manoeuvres should not be regarded as identical.
This distinction is clinically important rather than simply historical. Studies evaluating the diagnostic performance of “Rovsing sign” have used heterogeneous techniques, ranging from simple left lower quadrant pressure or percussion to deeper manipulation of the descending colon. Consequently, published estimates of sensitivity, specificity and likelihood ratios cannot be confidently attributed to the original Rovsing (1907) manoeuvre. The diagnostic performance of the original Rovsing sign, performed as described, therefore remains uncertain.
History of the Perman-Rovsing Sign
1871 – Ludwig Traube reported a patient with perforation of the appendix and peritonitis in whom the expected pain and tenderness in the right iliac region were absent. However, pain could be produced by palpatory pressure in the left iliac fossa [1871; I: 360-361].
Traube considered that the inflammatory process may have been situated too deeply to be reached by direct right-sided palpation. An early observation of pain provoked by contralateral abdominal pressure.
1904 – Emil S. Perman published Om indikationerna för operation vid appendicit samt redogörelse for å Sabbatsbergs sjukhus opererade fall. and detailed 244 cases of appendicitis between 1899-1904 at Sabbatsberg Hospital in Sweden. He described pain localised to the ileocaecal region produced by pressure on the left side of the abdomen during examination of patients with appendicitis.
Original
English
Därpå har jag äfven alltid funnit ett annat symtom tyda, nämligen en till ileocekaltrakten lokaliserad smärta vid tryck å vänstra delen af buken. Perman ES. 1904: 806
I have also always found another symptom to indicate this, namely pain localised to the ileocaecal region on pressure upon the left part of the abdomen. Perman ES. 1904: 806
A clinical example appears in case 154. A 25-year-old man with acute right-sided abdominal pain developed right iliac tenderness when pressure was applied to the left side of the abdomen. Operation revealed seropurulent intraperitoneal fluid and a small perforation at the tip of the appendix.
Perman later explained that he had discovered the phenomenon while beginning abdominal palpation away from the suspected inflammatory focus. In patients with appendicitis and periappendicitis, pressure on the left abdomen could produce pain at McBurney’s point without causing pain beneath the examining hand. He attributed this to mechanical transmission of pressure, displacement or traction toward the inflamed area rather than distension of the caecum.
1907 – Niels Thorkild Rovsing published Indirektes Hervorrufen des typischen Schmerzes an McBurney’s Punkt. Ein Beitrag zur Diagnostik der Appendicitis und Typhlitis [Indirect elicitation of the typical pain at McBurney’s point: a contribution to the diagnosis of appendicitis and typhlitis].
Rovsing described a specific manoeuvre intended to indirectly reproduce pain at McBurney’s point. The left hand was placed flat over the descending colon in the left iliac fossa. The right hand pressed the fingers of the left hand into the colon, which was compressed while the hand was moved upwards towards the left colonic flexure.
I press with my right hand onto the fingers of the left hand that is lying flat against the colon descendens [descending colon] and then let the hand glide up toward the splenic flexure…The entire method is based upon isolated rise of pressure within the colon.
Rovsing 1907
Rovsing proposed that this manoeuvre increased the pressure and tension of gas within the proximal colon. With the ileocaecal valve preventing decompression into the small bowel, he believed the resulting increase in pressure particularly affected the caecum and appendix, producing pain at McBurney’s point when either structure was inflamed.
He developed the manoeuvre in the autumn of 1904 after examining two patients with similar right iliac fossa pain in whom direct palpation was limited by pain and Dieulafoy’s défense musculaire. The indirect test produced severe pain at McBurney’s point in one patient, subsequently found to have appendicular peritonitis. It was negative in the second patient, whose appendix and bowel were normal at laparotomy. However, in this patient a retroperitoneal perirenal inflammatory process was subsequently identified.
Rovsing continued to use the manoeuvre for the following two years and reported experience in more than 100 cases. He proposed two principal applications. First, differentiating appendiceal or caecal disease from other causes of right iliac pain. Second, indirectly eliciting McBurney-point pain when direct palpation was difficult or potentially hazardous.
1908 – Carl Lauenstein published Zur Frage der Bedeutung des „Rovsing’schen Symptoms”. He questioned the specificity of the recently described “Rovsing symptom” after reporting a patient in whom palpation of the left lower abdomen produced pain in the right upper abdomen. Operation demonstrated acute suppurative gallbladder disease.
Lauenstein concluded that the phenomenon was not specific for appendicitis. However, his description of rapid, brief pressure or percussion over the left abdomen differed from Rovsing’s original technique of sustained compression of the descending colon directed proximally towards the left colonic flexure.
1908 – Arthur Hofmann published Zu dem Rovsing’schen Symptom reporting the results of testing Rovsing’s recently described sign in 34 patients over three months at the municipal hospital in Karlsruhe.
Among 18 patients with appendicitis/perityphlitis, the Rovsing symptom was present in only three. Hofmann also demonstrated positive responses in patients with pelvic and adnexal inflammatory disease, including bilateral pyosalpinx with purulent peritonitis. He concluded that the sign was unreliable both for diagnosing appendicitis and for distinguishing appendiceal inflammation from neighbouring pathology.
Hofmann also challenged Rovsing’s proposed intracolonic mechanism. The phenomenon could occur in patients who had previously undergone appendicectomy and could sometimes be elicited in the reverse direction, with right-sided pressure producing left-sided pain. He proposed that inflammation of the parietal peritoneum, together with transmitted pressure and traction through displaced bowel, mesentery and omentum, better explained the phenomenon than propagation of pressure through the colon.
He cautioned against relying upon the sign for operative decision-making, concluding that it could mislead rather than determine the diagnosis.
1908 – Rovsing responded immediately with Zu dem Rovsing’schen Symptom. Erwiderung an Dr. A. Hofmann. He emphasised that brief or rapid pressure over the left lower abdomen did not constitute his manoeuvre. The descending colon was to be isolated, compressed firmly against the posterior abdominal wall and, while maintaining compression, the examining hands moved slowly upwards towards the left colonic flexure. He summarised the principle of the test as an isolated increase of pressure within the colon.
Rovsing rejected peritonitis as the mechanism responsible for the sign, stating that it could be demonstrated particularly clearly in uncomplicated appendiceal inflammation without peritonitis.
He also addressed Lauenstein’s report of pain elicited in the right upper abdomen in a patient subsequently found to have gallbladder inflammation. Rovsing argued that the observation did not invalidate the principle of his test. Rather than producing pain at McBurney’s point, the manoeuvre had reproduced pain at the actual inflammatory focus in the right upper quadrant.
1908 – Ira Carleton Chase published A new test for the differential diagnosis of appendicitis, describing his “cecal distension test.” Deep pressure was applied to the left inguinal region and drawn upwards beneath the left costal margin to compress the descending colon and force its gaseous contents into the transverse and ascending colon. Further compression was intended to produce a “gaseous compression wave” reaching the caecum and provoking sharp right iliac pain when the caecum or appendix was inflamed.
Chase stated that he had independently developed the test approximately three years earlier and had subsequently demonstrated and taught it to his students. While preparing his paper, he reviewed Rovsing’s 1907 publicataion. Chase acknowledged the similarity, writing that “Rovsing and I have been working on the same idea,” while maintaining that his own technique and interpretation differed.
Unlike Rovsing, Chase did not consider distension itself painful. He proposed that caecal distension produced movement, induced peristalsis or traction upon inflamed appendiceal adhesions, thereby reproducing the characteristic pain.
1911 – Emil S. Perman returned to the subject in Uber die Bedeutung des indirekten Druckschmerzes bei Appendizitis [On the significance of indirect pressure pain in appendicitis]. He confirmed that he had known and used the phenomenon long before Rovsing’s 1907 publication and reproduced his original 1904 description of ileocaecal pain produced by pressure on the left abdomen.
Perman explained that he had discovered the phenomenon while beginning abdominal palpation away from the suspected inflammatory focus. He attributed the pain to pressure, displacement, stretching or jarring transmitted directly across the abdomen towards the inflamed area, rather than Rovsing’s proposed movement of colonic contents and distension of the caecum. Attempts to reproduce pain using Rovsing’s specific compression manoeuvre when simple pressure was negative had been unsuccessful.
Perman reported experience from a large clinical series. Between June 1904 and December 1910 his department had operated on 1,104 patients with appendicitis, including 813 acute cases. He associated indirect pressure pain with more advanced pathological changes such as phlegmonous inflammation, gangrene and impending perforation. Perman regarded a positive finding as an indication for prompt operation. However, he acknowledged that the sign had been positive in cases of cholecystitis, suppurative salpingitis and pelvic peritonitis and the sign was not specific for appendicitis.
1931 – Carl Wallerström published Om diagnosen av den akuta appendiciten. He reviewed the diagnostic value of the Rovsing symptom in 211 surgically confirmed cases of acute appendicitis treated at Växjö Hospital between 1929 and 1931. His technique and proposed mechanism followed Perman more closely than Rovsing. He initially observed left-sided pressure alone and that adding Rovsing’s original pressure-and-massage technique did not convert a negative test to positive. Wallerström suggested “Perman’s symptom” might be the more appropriate name. However he retained the eponym of Rovsing as it was his paper that stimulated the ongoing discussion.
Wallerström recorded an overall positive test in 70% (147/211) of cases [mild appendicitis (63%), severe uncomplicated disease (78%) and gangrenous appendicitis (75%)]. He found the test most useful when other classical features were absent. In 17 patients with no local tenderness or guarding, 11 nevertheless had a positive indirect pressure sign. He concluded that any intra-abdominal inflammatory process might produce the symptom, a negative sign did not exclude appendicitis, and a positive response provided supportive evidence (particularly of advanced or complicated appendicitis).
1956 – W. W. Davey evaluated Rovsing’s sign in 303 consecutive, surgically confirmed cases of acute appendicitis. The sign was positive in only 5/303 (1.7%). Three additional patients had a positive sign without appendicitis but with another inflammatory lesion in the right iliac fossa.
Davey directly tested Rovsing’s proposed mechanism. Manometric experiments on colon obtained at necropsy demonstrated no increase in intracaecal pressure following distal colonic compression unless the colon was already distended. Radiological observations similarly failed to demonstrate movement of gas towards the caecum during left-sided pressure. He concluded that Rovsing’s proposed intracolonic pressure mechanism was incorrect.
In each of Davey’s five positive appendicitis cases the inflamed appendix was in contact with the parietal peritoneum of the anterior abdominal wall. Local anaesthesia abolished the Rovsing response in three patients. Davey proposed that left-sided pressure produced movement or vibration across the abdomen, causing temporary friction between an inflammatory lesion and adjacent parietal peritoneum. He concluded that the sign was uncommon and could not distinguish appendicitis or caecal inflammation from other inflammatory lesions of the right iliac fossa.
2014 – Prosenz and Hirtler published Rovsing sign revisited-effects of an erroneous translation on medical teaching and research. They reviewed Rovsing’s original 1907 description and investigated how Rovsing’s sign was represented in contemporary literature.
They identified 57 publications using the term Rovsing sign. Of these only 14 described how the manoeuvre was performed, and none reproduced Rovsing’s original technique correctly. Three contemporary English surgical textbooks also described it incorrectly, whereas all three German surgical texts and three German anatomy texts retained the original antiperistaltic compression manoeuvre.
The authors proposed that translation and subsequent abbreviation of Rovsing’s description contributed to the change from his original technique of compression-massage to simple palpation or pressure in the left lower quadrant. As a result, much of the published diagnostic literature may have evaluated a manoeuvre different from that originally described by Rovsing. Reported sensitivity ranged from 19–75%, specificity from 58–93% and likelihood ratios from 1.5–4.23, but the authors argued that these figures could not reliably establish the diagnostic performance of the original sign because of inconsistent technique.
Associated Persons
- Ludwig Traube (1818-1876)
- Emil S. Perman (1856-1946)
- Niels Thorkild Rovsing (1862-1927)
- Walter Arthur Bastedo (1873-1952)
References
Original articles
- Traube L. Epicritische Bemerkungen in: Gesammelte Beitrage zur Pathologie und Physiologie. 1871
- Perman ES. Om indikationerna för operation vid appendicit samt redogörelse for å Sabbatsbergs sjukhus opererade fall. Hygiea 1904; 66(2): 797-847 [Perman symptom p806] Translation: Mads Advastad
- Rovsing T. Indirektes Hervorrufen des typischen Schmerzes an McBurney’s Punkt. Ein Beitrag zur Diagnostik der Appendicitis und Typhlitis [Indirect elicitation of the typical pain at McBurney’s point. A contribution to the diagnosis of appendicitis and typhlitis]. Zentralblatt für Chirurgie 1907; 34: 1257-59
- Lauenstein C. Zur Frage der Bedeutung des „Rovsing’schen Symptoms”. Zentralblatt für Chirurgie 1908; 35: 233–4
- Hoffmann A. Zu dem Rovsing’schen Symptom. Zentralblatt für Chirurgie 1908; 35: 537–8.
- Rovsing T. Zu dem Rovsing’schen Symptom. Erwiderung an Dr. A. Hofmann. Zentralblatt für Chirurgie 1908; 35: 537–8.
- Chase IC. A new test for the differential diagnosis of appendicitis. JAMA. 1908;L(8):610–611.
- Perman ES. Uber die Bedeutung des indirekten Druckschmerzes bei Appendizitis. Zentralblatt für Chirurgie. 1911; 38(2): 1593-1596
- Bastedo WA. The dilatation test for chronic appendicitis. American Journal Of The Medical Sciences. 1911; 142: 11-14 [Bastedo sign]
Review articles
- Indirect production of typical pain at McBurney’s point. JAMA 1907; XLIX: 1882.
- Hertz AF. Bastedo’s sign: A new sign of chronic appendicitis. Lancet 1913; 181(4673): 816-817
- Wallerström C. Om diagnosen av den akuta appendiciten, särskilt med hänsyn till det s k Rovsings symtom. Svenska läkartidningen. 1931; 28: 1385-98.
- Davey WW. Rovsing’s sign. Br Med J. 1956; 2(4983): 28-30.
- Smith PH. The Diagnosis of Appendicitis. Postgrad Med J. 1965 Jan; 41(471): 2–5.
- Räf L. Skandinaviska kirurger först med beskrivning av tecken på appendicit [The men behind the syndrome: Emil Perman and Nils Thorkild Rovsing. Scandinavian surgeons were the first to describe signs of appendicitis] Läkartidningen 1984; 81(32-33): 2829-30
- Lewis, SRR. Appendicitis BMJ 2011; 343: d5976
- Hognason K, Swan KG. Niels Thorkild Rovsing: the Surgeon Behind the Sign. Am Surg 2014 12; 80(12): 1201-1206
- Prosenz J, Hirtler L. Rovsing sign revisited-effects of an erroneous translation on medical teaching and research. J Surg Educ. 2014 Sep-Oct;71(5):738-42
- McKennedy C. Rovsing sign. Eponym A Day. Instagram
- McKennedy C. Perman-Rovsing sign. Eponym A Day. Instagram
- Eponymythology: Appendicitis eponymous signs. LITFL
eponymictionary
the names behind the name

Faizan Malik is an RMO in the ED at Sir Charles Gairdner Hospital in Perth. A University of Leeds MBChB graduate, he traded Yorkshire rain for Australian sunshine and beaches. He’s pursuing a career in medicine, drawn to the complexity, chaos and conundrums that come with it

BA MA (Oxon) MBChB (Edin) FACEM FFSEM. Emergency physician, Sir Charles Gairdner Hospital. Passion for rugby, medical history, medical education, and asynchronous learning #FOAMed evangelist. Editor-in-Chief and Webmaster of Life in the Fast lane, LITFL | On Call 4e| Eponyms | Books | Horology |
Emil Perman was the first to describe the symptom and give the true explanation ( Henri Sundberg 1917)