


The Macintosh laryngoscope is a curved-blade direct laryngoscope introduced by Sir Robert Reynolds Macintosh in 1943.
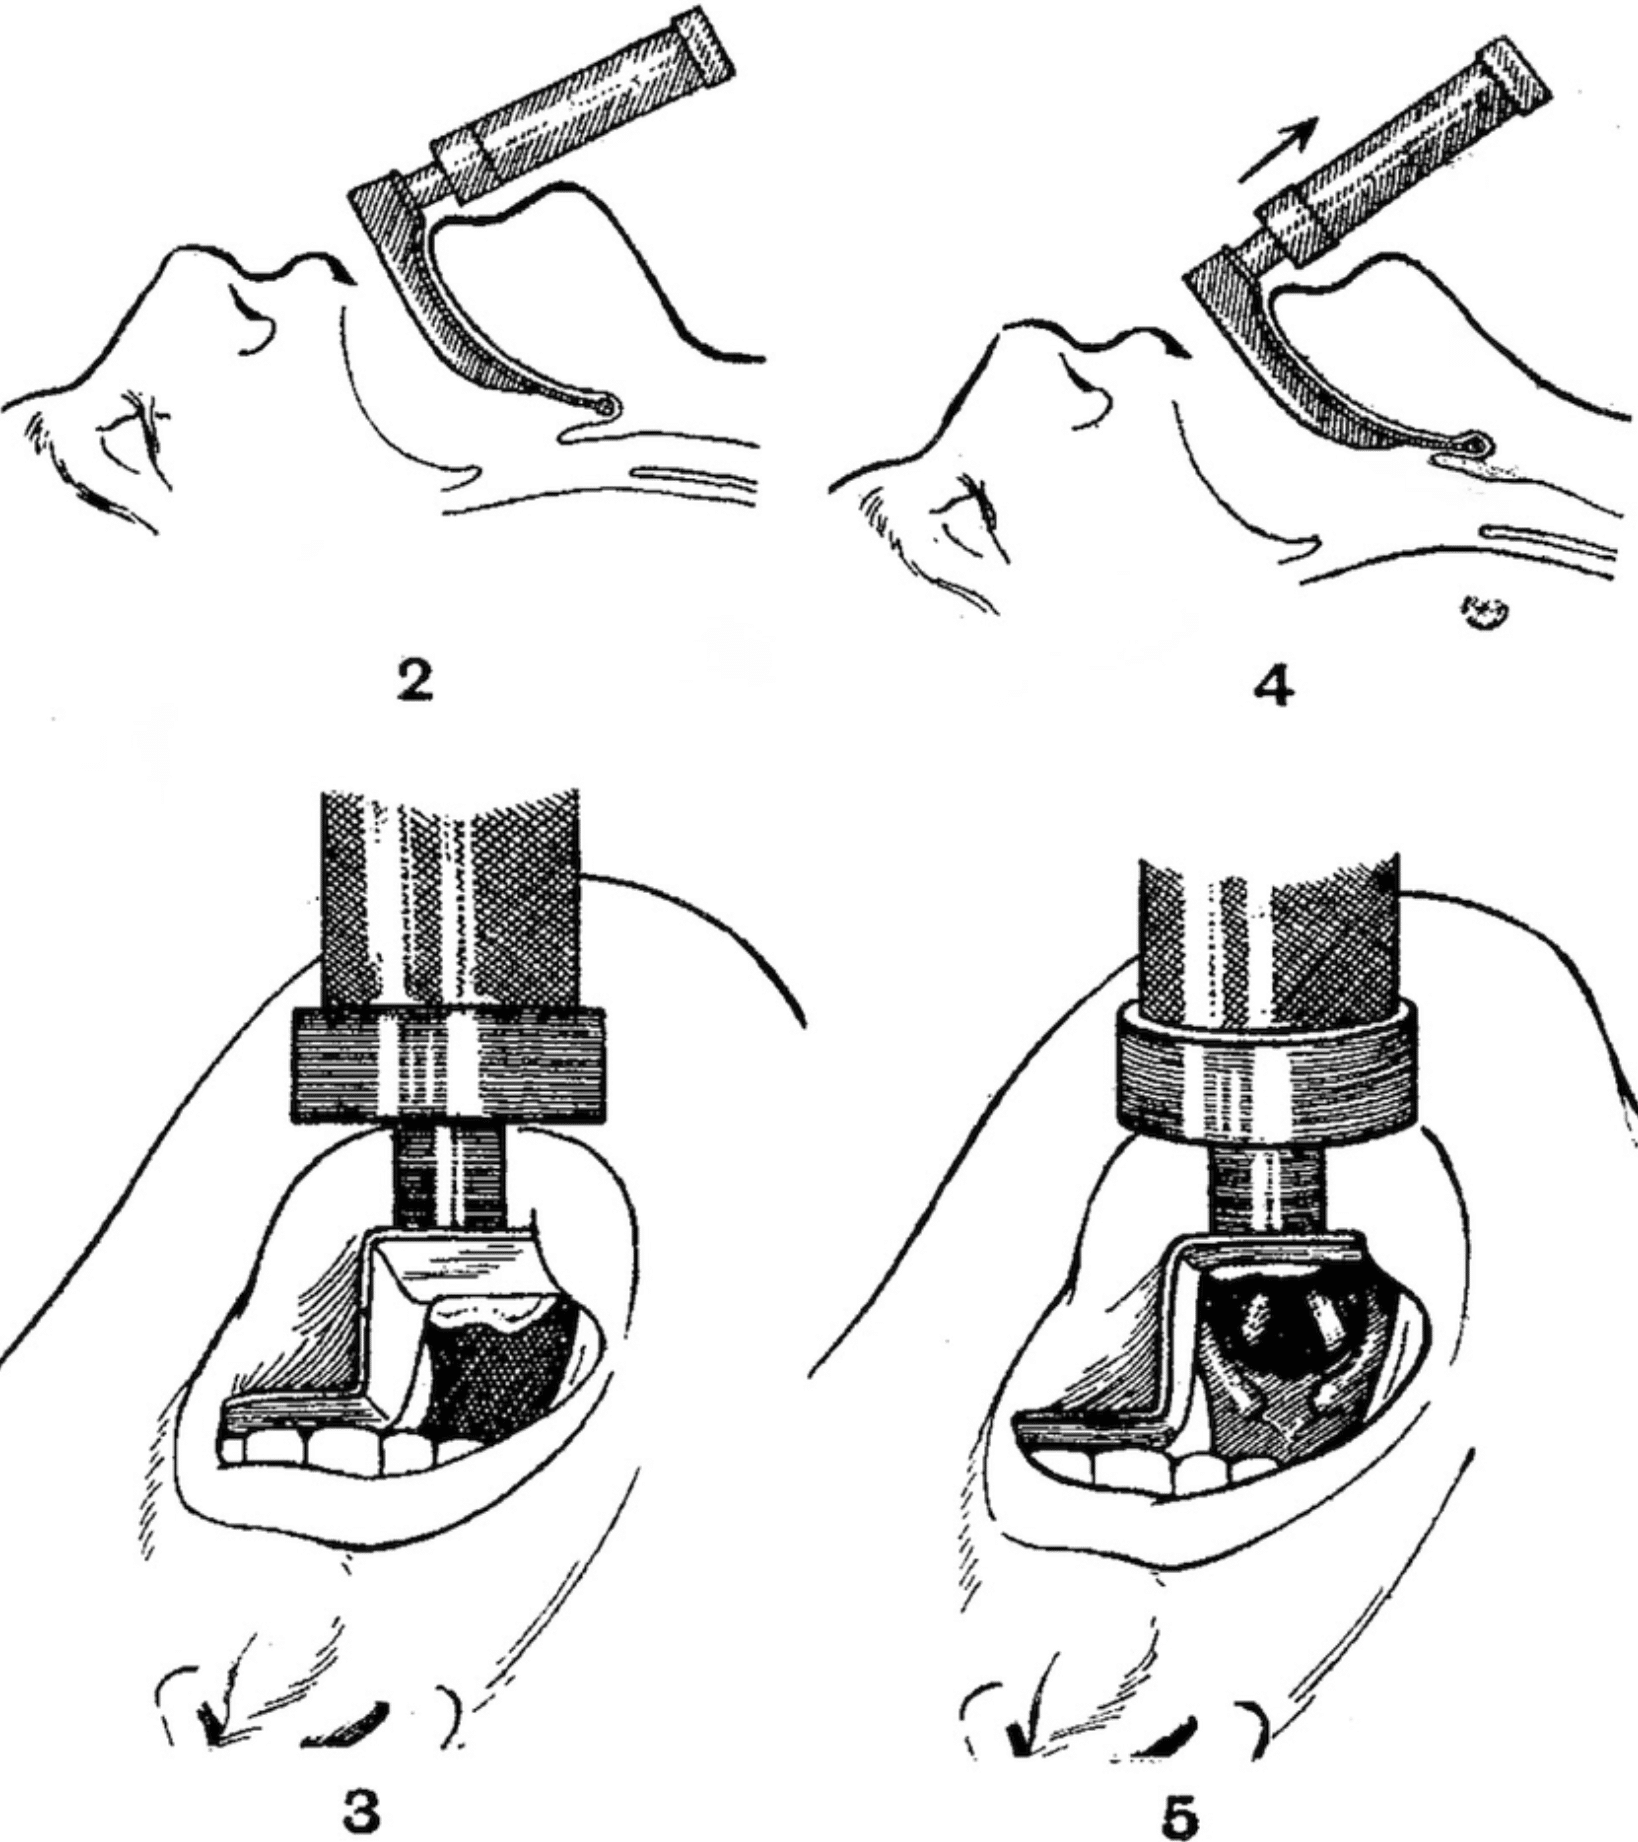
The defining innovation was not the curvature itself, but the shorter blade and deliberate placement of its tip in the vallecula, proximal to the epiglottis. Elevation of the blade lifts the tongue and indirectly elevates the epiglottis through its attachment to the tongue, exposing the glottis without directly levering the epiglottis itself.
The technique was particularly useful before neuromuscular blocking drugs became routine, when direct stimulation of the epiglottis could provoke laryngospasm and other vagal reflexes. The Macintosh pattern became one of the most widely used direct laryngoscope blades in anaesthetic practice.
Description
The Macintosh blade is curved throughout much of its length and terminates in a rounded distal tip positioned in the vallecula.
Rather than passing beyond the epiglottis and directly lifting it, as with straight laryngoscopes, the blade elevates the tongue and adjacent tissues. Tension transmitted raises the epiglottis indirectly and brings the larynx into view.
The blade is conventionally introduced from the right side of the mouth, sweeping the tongue to the left before the tip is placed in the vallecula.
the Macintosh laryngoscope…probably the most successful ‘durable’ in the history of anaesthesia to date.
Sir Anthony Jephcott, 1983

Fig 1A. This laryngoscope is designed to lessen the difficulty of exposing the larynx to pass an endotracheal tube. Normally the long straight blade of the standard laryngoscope is passed beyond the epiglottis in order to evert it.
Fig 1B The new laryngoscope is designed so that when its short curved blade is in position the tip will fit into the angle made by the epiglottis with the base of the tongue. Macintosh, Lancet 1943
Historical development
1941 – Robert Reynolds Macintosh published An improved laryngoscope. This earlier instrument incorporated an epiglottis retractor and a modified illumination system. Macintosh regarded the modifications as only a limited improvement, and the design was not the eponymous Macintosh blade.
1943 – During a tonsillectomy list at Oxford, Macintosh observed that using the Boyle-Davis mouth gag produced a surprisingly clear view of the vocal cords. His senior technician Richard Salt was present and, before the end of the operating list, had soldered a Davis-type blade onto a laryngoscope handle.
The key feature was that the blade tip terminated proximal to the epiglottis, rather than passing behind it. Before the widespread use of neuromuscular blocking drugs, tracheal intubation often required deep general anaesthesia. Direct elevation of the epiglottis could provoke laryngospasm, bradycardia and hypotension. By placing the blade in the vallecula rather than directly manipulating the epiglottis, Macintosh believed that the larynx could be exposed at a lighter plane of anaesthesia with less reflex stimulation.
Macintosh published A new laryngoscope in the Lancet on February 13, 1943. He described his short curved blade whose tip fitted into the angle between the epiglottis and the base of the tongue. Elevation of the instrument displaced the tongue upwards and drew the epiglottis with it, exposing the larynx.
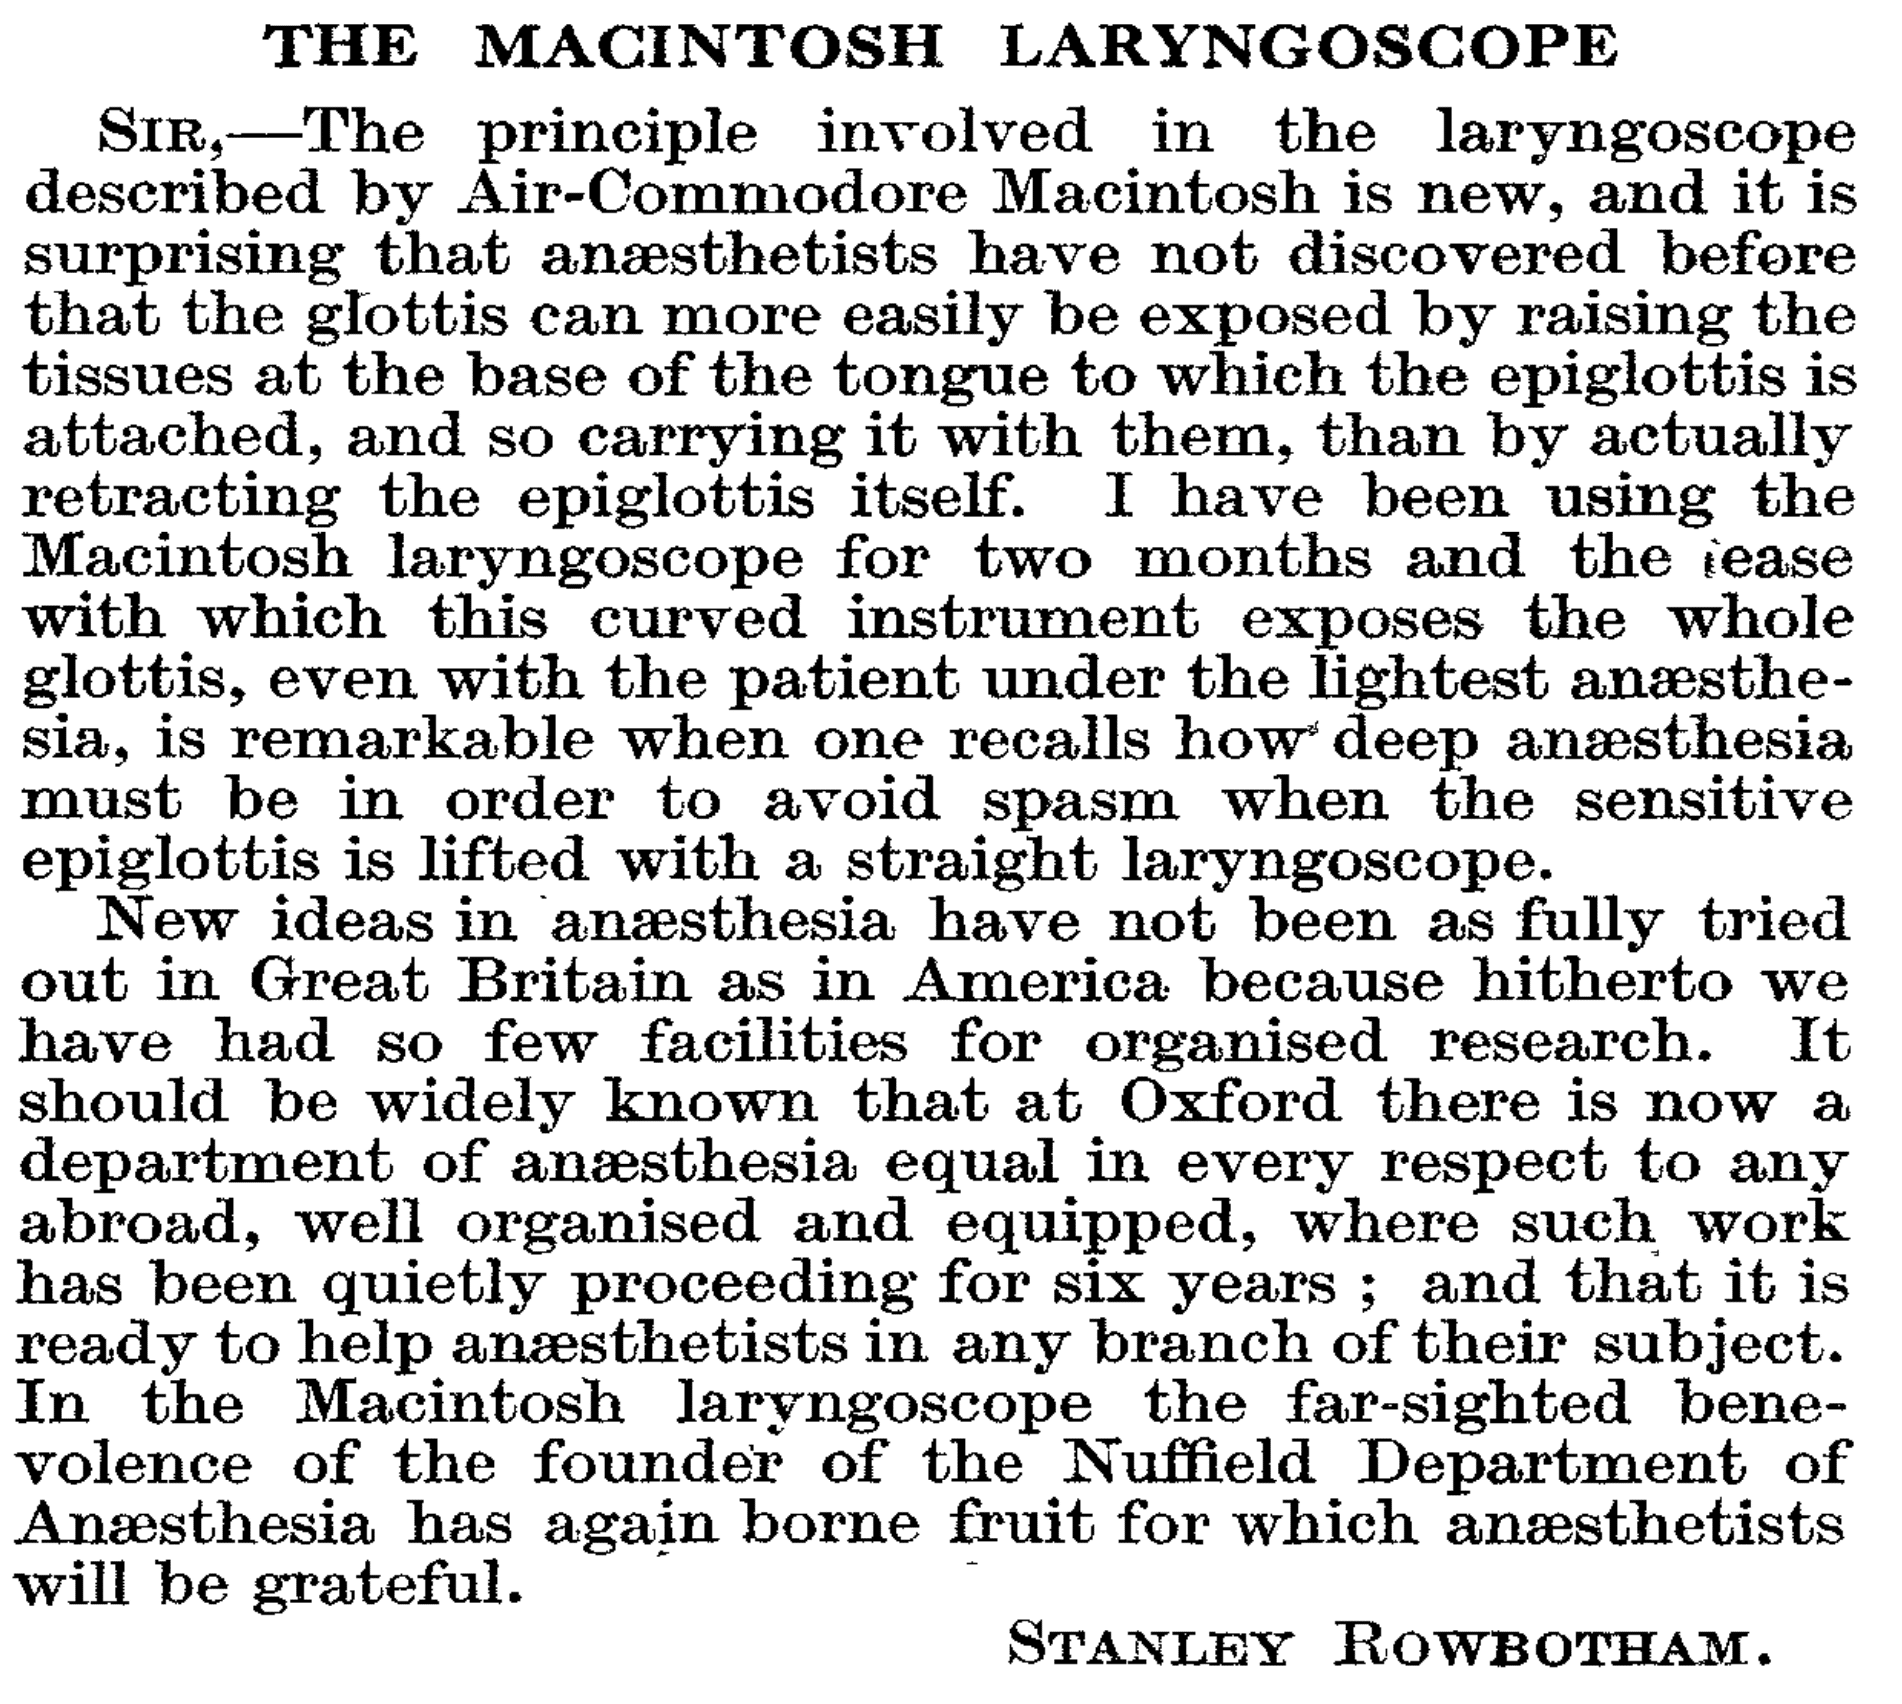
In the following edition of the Lancet, Stanley Rowbotham referred to the instrument as The Macintosh laryngoscope. He reported that it exposed the glottis remarkably easily even at light levels of anaesthesia.
The curve was convenient, but “not of primary importance.”
Macintosh had used blades ranging from markedly curved to completely straight and found little difference when they were of appropriate length and correctly positioned. He preferred a curved blade largely because it was easy to introduce and accommodated the natural curvature of the Magill-type endotracheal tube.
The precise shape or curve of the blade does not seem to matter much provided that the tip does not go beyond the epiglottis.
Manufacture and dissemination
1943 – Medical and Industrial Equipment Ltd initially manufactured the new laryngoscope. At Oxford, three university technicians established the Longworth Scientific Instrument Company, later Penlon, and started manufacturing Macintosh laryngoscopes within months.
Macintosh also sent one of Richard Salt’s handmade instruments to Richard Foregger in New York. Foregger recognised its potential and began manufacture in the United States.
Unknown to Macintosh, the Foregger Company filed a US patent in August 1943, naming Macintosh as inventor. The patent was granted in July 1944. The patent drawings carried a signature apparently added by the patent attorney, who also misspelled his name ‘MacIntosh‘.
Macintosh did not seek patent protection elsewhere and received no royalties from the instrument. He later joked that, given the millions of blades eventually sold, even a small royalty would have made him a millionaire.
The availability of inexpensive Longworth instruments in Britain and rapid manufacture by Foregger in the United States contributed greatly to international adoption.

Blade sizes and later forms
Macintosh originally designed two blade sizes, one for an adult and one for a child.
The original adult blade approximated the modern Macintosh size 3. Macintosh later recalled that the prototypes had largely been tested in women undergoing gynaecological surgery and the standard blade proved too short for some patients. A larger adult blade, corresponding to the size 4, was added by Longworth in 1951.
Manufacturers later introduced additional sizes and developed two principal descendants of the original design:
- the American A-Mac, derived largely from the Foregger form
- the English E-Mac, descended from the Longworth pattern
The Macintosh laryngoscope was revolutionary not because it was curved, but because it made indirect elevation of the epiglottis a deliberate and reproducible technique.
Eponymythology
The instrument was introduced by Macintosh in 1943 as “A new laryngoscope.” The eponymous term was bestowed by his contemporaries rather than by Macintosh himself. Shortly after the original publication, Rowbotham wrote to the Lancet under the heading “The Macintosh Laryngoscope”, describing his early clinical experience with the instrument.
The history of the device illustrates how an eponymous term can obscure collaborative development. Macintosh identified the clinical principle, but it was Richard Salt who converted the observation into a functional instrument. Manufacturers including Medical and Industrial Equipment, Longworth and Foregger later shaped the commercial forms that spread internationally.
Historical misconceptions
“Macintosh invented the laryngoscope in 1941.”
No. His 1941 improved laryngoscope was a different instrument incorporating an epiglottis retractor. The eponymous Macintosh laryngoscope was described in 1943.
“The innovation was the curved blade.”
No. Macintosh repeatedly emphasised that the curve was secondary. The essential feature was a blade short enough for its tip to remain proximal to the epiglottis and elevate it indirectly.
“The curve was introduced primarily to protect the upper teeth.”
This has been repeated in later historical reviews, but Macintosh stated that improved exposure of the larynx was the primary objective. Reduced risk of dental trauma was an advantage, not the principal rationale.
“Macintosh discovered indirect elevation of the epiglottis.”
This overstates the priority. John Urban Human had advocated advancing the laryngoscope only until the epiglottis came into view, and Macintosh had observed Margaret Hawksley successfully using a similar approach in infants. Macintosh’s contribution was to make deliberate vallecular placement and indirect elevation of the epiglottis the organising principle of a purpose-designed laryngoscope.
One morning during a tonsillectomy list, I had a bit of luck and the nous to take advantage of it. On opening a patient’s mouth with a Boyle-Davis gag I found the cords perfectly displayed. Richard Salt (a really excellent chap) was in the theatre with me; before the morning had finished he had gone out and soldered a Davis blade on to a laryngoscope handle and this functioned quite adequately as a laryngoscope. The important point being that the tip finishes up proximal to the epiglottis. The curve, although convenient when intubating with naturally curved tubes, is not of primary importance as I emphasised subsequently
Macintosh 1983
Associated persons
- Richard Salt – senior technical assistant in the Nuffield Department of Anaesthetics who constructed the first prototype.
- John Urban Human (1897/1898 – 1948)
- Sir Robert Reynolds Macintosh (1897–1989)
- Stanley Rowbotham (1890–1979) – British anaesthetist who publicly called the instrument the Macintosh laryngoscope.
- Richard von Foregger (1872–1960) – instrument manufacturer responsible for rapid commercial production and distribution in the United States.
Alternative names
- Macintosh blade
- Mac blade
- Mac laryngoscope
References
Original articles
- Macintosh RR. An improved laryngoscope. Br Med J 1941; 2: 914
- Human JU. Blind intubation and the signs of anaesthesia. John Bale Medical Publications Ltd, London 1941.
- Macintosh RR. A new laryngoscope. Lancet 1943; 241(6233): 205
- Rowbotham S. The Macintosh laryngoscope. Lancet 1943; 241(6234): 253
- Macintosh RR. Laryngoscope blades. Lancet 1944; 243(6293): 485
- Patented July 25, 1944 Laryngoscope. Robert R. MacIntosh, Oxford, England, assignor to The Foregger Company
Review articles
- Jephcott A. The Macintosh laryngoscope. A historical note on its clinical and commercial development. Anaesthesia. 1984; 39(5): 474-9
- Jephcott A. A History of Longworth Scientific Instrument Co. Ltd. 1988
- McIntyre JW. Laryngoscope design and the difficult adult tracheal intubation. Can J Anaesth. 1989 Jan;36(1):94-8.
- Burkle CM et al. A Historical Perspective on Use of the Laryngoscope as a Tool in Anesthesiology. Anesthesiology 2004; 100(4): 1003-1006.
- McCoy EP, Mirakhur RK. The levering laryngoscope. Anaesthesia. 1993 Jun;48(6):516-9.
- Minassian H et al. Robert Reynolds Macintosh, M.D. (1897-1989): Forefather of Anesthesiology, Advocate for Patient Safety. 2017
- Scott J, Baker PA. How did the Macintosh laryngoscope become so popular? Paediatr Anaesth. 2009 Jul;19 Suppl 1:24-9.
- Ball CM, Westhorpe RN. Early laryngoscopes for anaesthesia. Anaesth Intensive Care. 2014 Nov;42(6):687-8.
Eponym
the person behind the name

BA MA (Oxon) MBChB (Edin) FACEM FFSEM. Emergency physician, Sir Charles Gairdner Hospital. Passion for rugby, medical history, medical education, and asynchronous learning #FOAMed evangelist. Editor-in-Chief and Webmaster of Life in the Fast lane, LITFL | On Call 4e| Eponyms | Books | Horology |