


Stepwise approach to video laryngoscopy
A structured approach to recognising airway landmarks, positioning the laryngoscope and delivering the endotracheal tube.
Successful laryngoscopy is a sequence of anatomical recognition and technical manoeuvres that begins with controlled blade insertion and ends only after the endotracheal tube has passed safely through the glottis.
Here we break the process of laryngoscopy down into reproducible stages to provide a framework for learning the procedure, troubleshooting difficulties and reviewing recorded attempts. This post describes the portion of the intubation visible during video laryngoscopy, from blade entry to confirmed passage of the endotracheal tube through the glottis. For each stage we outline:
- The goal: what is the operator trying to achieve
- What to look for: anatomical or video landmark
- Common problems: what often goes wrong
- Corrective manoeuvres: what to do about it
1. Blade entry and tongue control
Effective laryngoscopy begins before the glottis comes into view. Controlled blade entry, tongue displacement and early management of contamination help create the best working environment.
Goal: Introduce the laryngoscope smoothly while controlling the tongue and maintaining a deliberate trajectory toward the midline airway.
Look for: Tongue displaced away from the working channel; progressive visualisation of oral and pharyngeal structures; a clear camera view. Early use of suction when required.
Common problems: Blade tip obstructed by teeth or tongue. Inadequate tongue control. Contamination obscuring the lens or airway. Lateral blade trajectory.
Corrective manoeuvres: Withdraw and redirect if entry is obstructed and improve tongue displacement. Suction before advancing through an obscured field. Re-establish a controlled midline trajectory.
Relevant performance errors: Blade-tip entry error · poor tongue control · inadequate suction · insertion off midline
2. Establish orientation
Do not advance blindly in search of the vocal cords. Maintain orientation by recognising structures sequentially and using each landmark to guide the next movement of the blade.
Uvuloscopy → Epiglottoscopy → Valleculoscopy
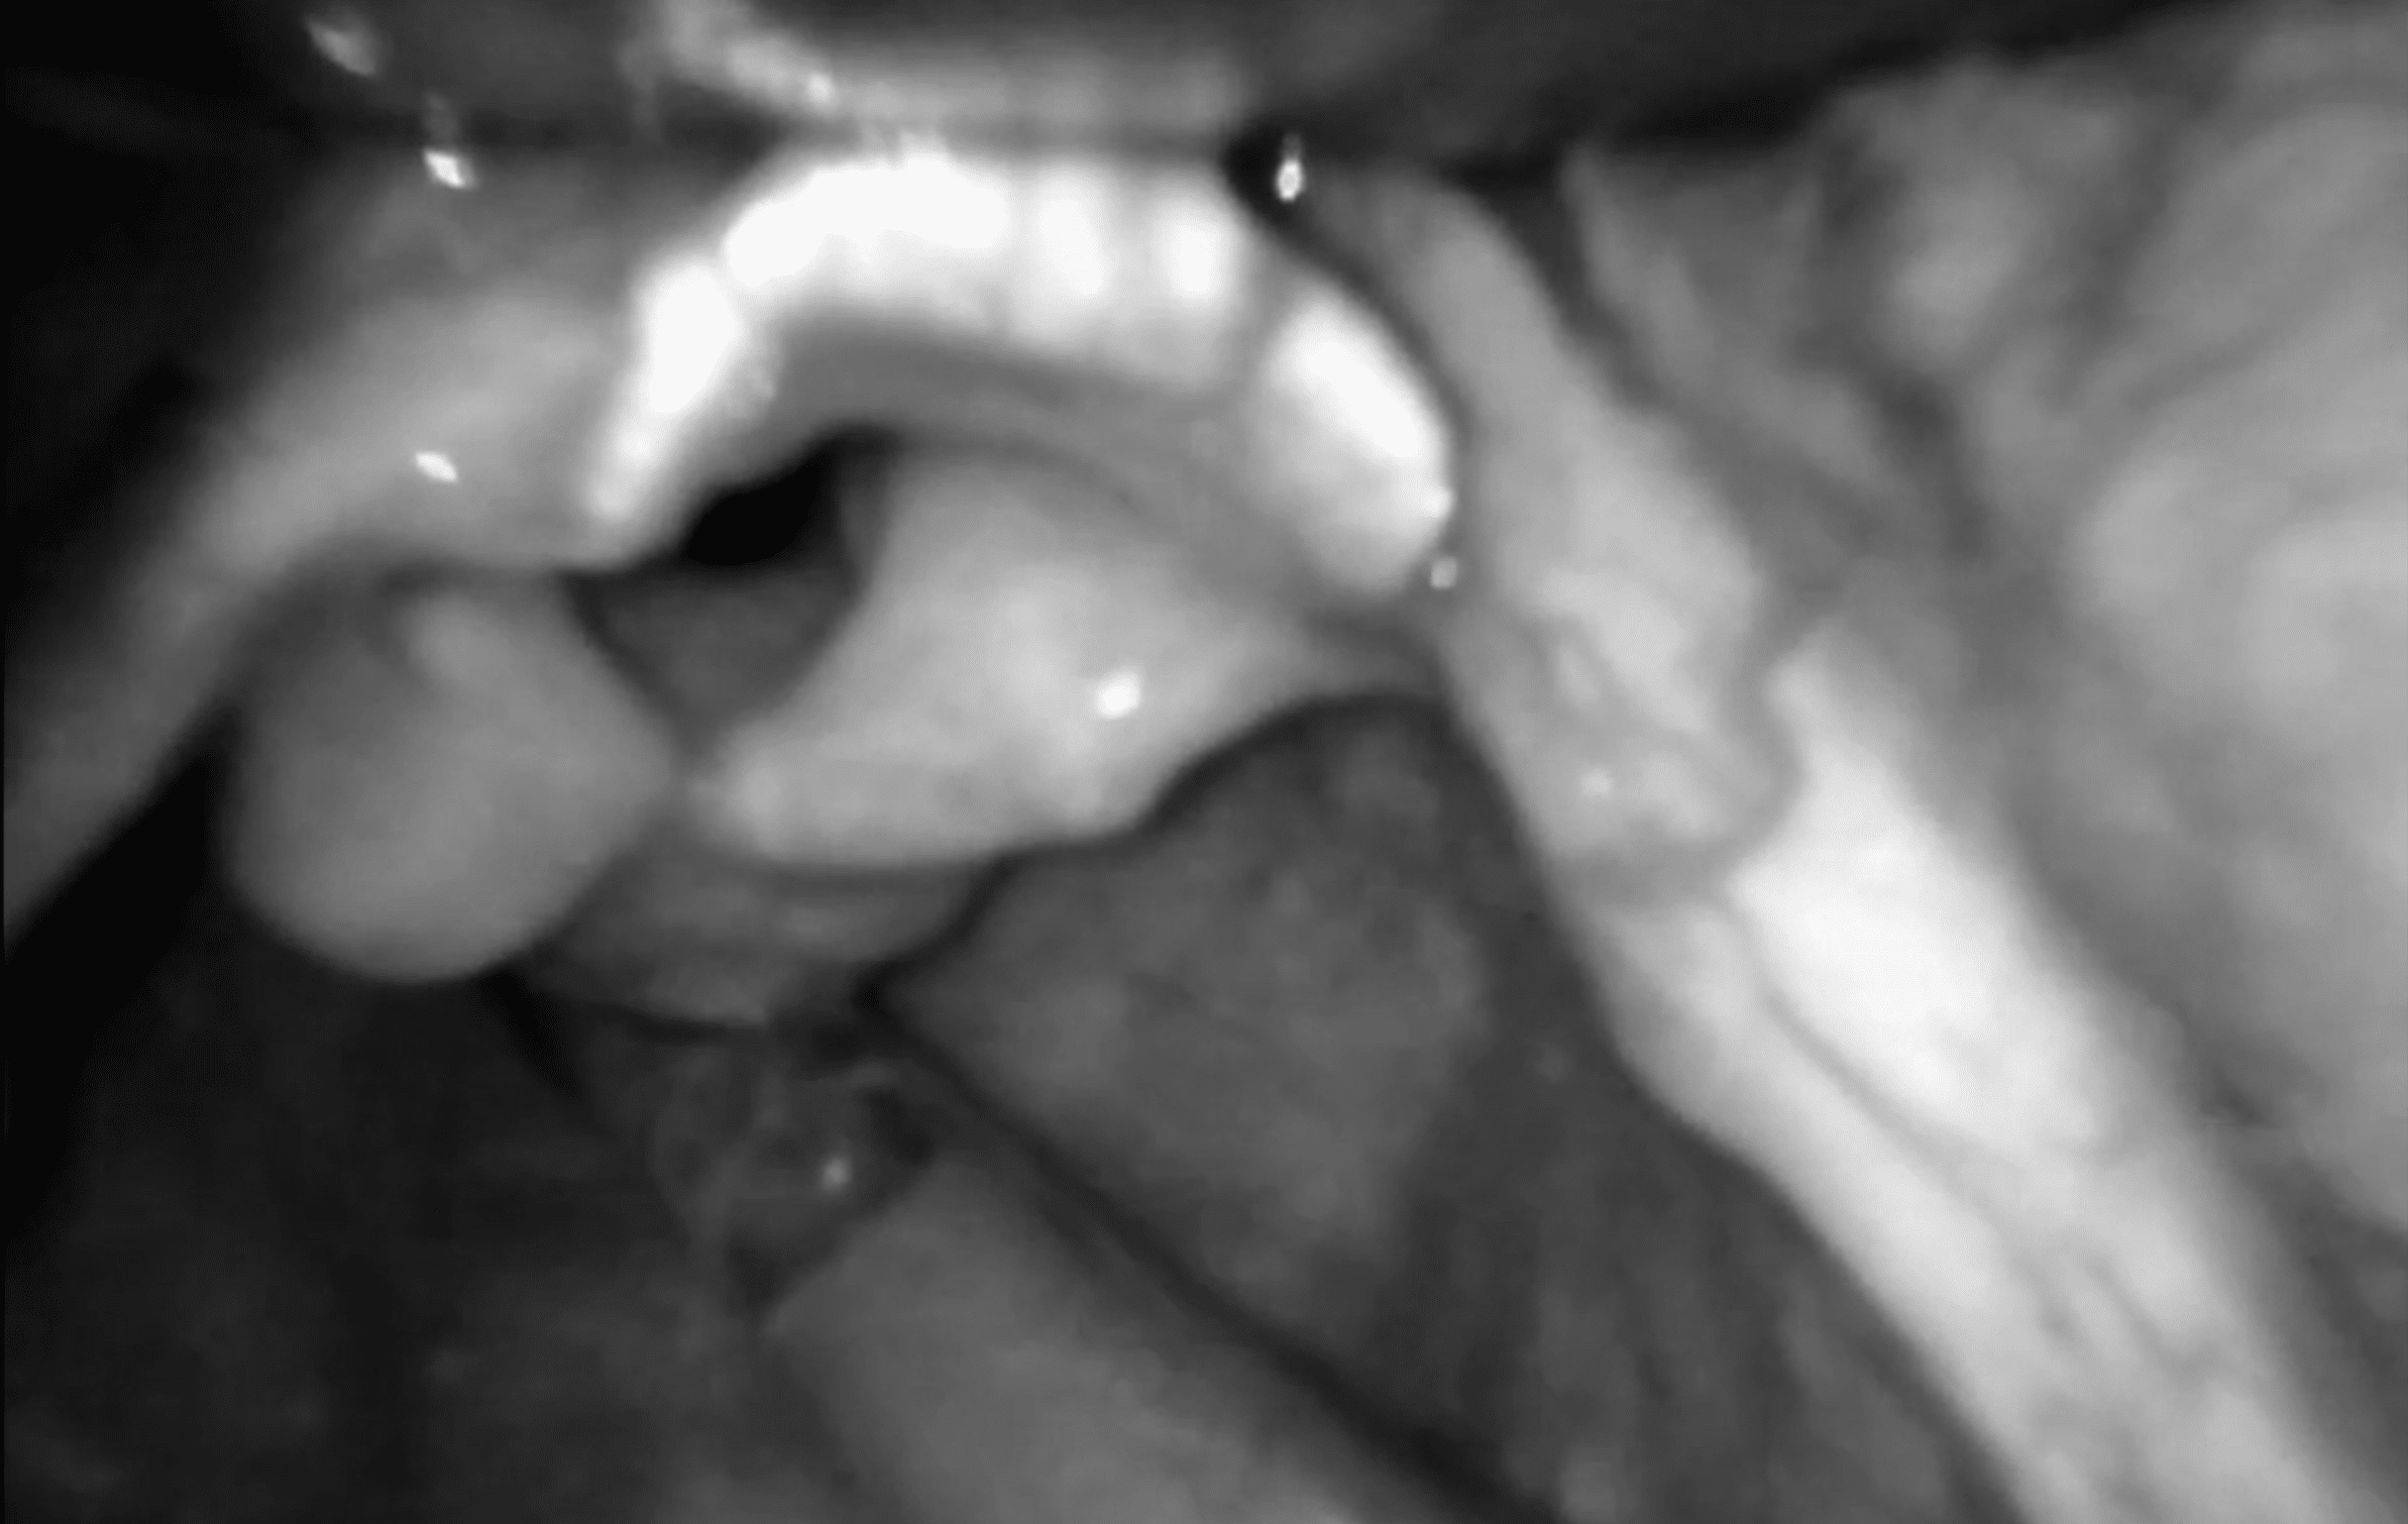
The uvula may provide an early midline landmark, followed by identification of the epiglottis and then the vallecula. Not every structure will be visible in every attempt. The principle is stepwise anatomical recognition.
Goal: Maintain spatial orientation by recognising airway structures sequentially rather than advancing blindly in search of the vocal cords.
Look for: Tongue and palate → uvula if visible → epiglottis → vallecular or laryngeal structures.
Common problems: Rapid advancement; loss of midline; failure to recognise visible structures; oesophageal visualisation after overrunning the laryngeal inlet.
Corrective manoeuvres: Slow blade advancement; return to the last recognised landmark; re-centre the blade; withdraw if anatomy has been overrun.
Relevant performance errors: Missed anatomical structure recognition · insertion off midline · overly deep insertion
3. Identify the epiglottis
The epiglottis is the pivotal landmark for establishing orientation in the lower pharynx. Once identified, its position, shape and relationship to the blade determine whether the operator should proceed to vallecular engagement or direct epiglottic elevation.
Goal: Identify the epiglottis and determine its position and relationship to the blade before attempting final blade placement.
Look for: Epiglottic edge and shape and midline relationship. Look for the vallecula where visible and identify anatomical variation or distortion.
Common problems: Epiglottis not recognised. Blade passed lateral to it; overly deep insertion; omega-shaped, floppy, oedematous or distorted epiglottis.
Corrective manoeuvres: Withdraw until the epiglottis reappears. Re-centre. Suction away obscuring material. Alter the approach when anatomical variation prevents normal positioning.
Relevant performance errors: Missed anatomical structure recognition · overly deep insertion · insertion off midline
4. Position the blade tip
Blade-tip position determines how the epiglottis will be elevated. With Macintosh-style techniques, the blade is seated in the vallecula to elevate the epiglottis indirectly. With a Miller blade or Mac-as-Miller technique, the epiglottis is elevated directly.
a. Vallecular technique
Goal: Seat the blade tip securely in the midline vallecula so that lifting translates the epiglottis anteriorly.
Look for: Median glossoepiglottic fold; centred blade tip; epiglottic translation with lift.
Common problems: Off-midline position; inadequate depth; lost seating; excessive vallecular pressure.
Corrective manoeuvres: Re-centre; advance or withdraw slightly; restore vallecular seating; lift rather than rotate.
Relevant performance errors: Failure to engage midline vallecula · not fully seated · lost seating · too much force in vallecula
b. Direct epiglottic elevation
Goal: Position the blade beneath the epiglottis and elevate it directly when using a straight-blade or deliberate direct-lift technique.
Look for: Controlled capture and elevation of the epiglottis without loss of orientation.
Common problems: Accidental epiglottic override; excessive depth or rotation; poor device-delivery geometry.
Corrective manoeuvres: Withdraw and reposition; distinguish intentional direct elevation from inadvertent override.
Relevant performance errors: overriding the epiglottis (when unintended) · excessive depth/rotation, with the caveat that deliberate direct epiglottic elevation is not itself an error.
5. Optimise glottic exposure
The most useful view is one that provides sufficient laryngeal exposure for device delivery. Blade depth, lift, rotation and external laryngeal manipulation should be adjusted with tube passage.
Goal: Obtain sufficient glottic exposure for safe device delivery while maintaining stable blade position and workable geometry.
Look for: Vocal folds, arytenoids and glottic opening; stable laryngeal view; adequate space for bougie or tube delivery.
Common problems: Inadequate lift; excessive blade rotation; overly close camera position; contamination; unstable vallecular seating.
Corrective manoeuvres: Adjust lifting force and direction; optimise depth; restore blade seating; suction; use external laryngeal manipulation when appropriate.
Relevant performance errors: Inadequate lifting force · over-rotated insertion · lost vallecular seating · inadequate suction
Then describe the best view obtained with modified Cormack–Lehane (Yentis–Lee) and/or POGO, as appropriate.
Note: a usable Grade II view with appropriate access for tube delivery may be preferable to aggressively chasing a prettier Grade I camera image.
6. Deliver the airway device
At this stage the techniques diverge. Standard-geometry video laryngoscopy (SGVL) generally provides a direct delivery path, whereas hyperangulated video laryngoscopy (HAVL) requires the tube to negotiate the curvature between the mouth and the visualised glottis.
a. Standard-geometry video laryngoscopy (SGVL)
Typical pathway: bougie or tube → glottic inlet → trachea
Goal: Direct the bougie or endotracheal tube through the glottic opening while maintaining the laryngoscopic view.
Look for: Controlled approach to the vocal folds; passage through the glottis; response to resistance.
Common problems: Bougie misdirection; anterior tracheal-ring hold-up; arytenoid impingement; loss of lift during delivery.
Corrective manoeuvres: Redirect or rotate the introducer/tube; withdraw slightly before re-advancing; maintain blade position and glottic exposure.
Relevant performance errors: Bougie delivery issue · tube delivery issue
b. Hyperangulated video laryngoscopy (HAVL)
Typical pathway: shaped tube + rigid stylet → controlled rotation toward glottis → advance tube → progressively withdraw stylet
Goal: Deliver the shaped styleted tube using controlled rotation and maintain tube position during stylet withdrawal.
Look for: Tube approaching the glottis on an appropriate trajectory; controlled rotation; passage beyond the cords; stable tube during stylet removal.
Common problems: Posterior translation rather than rotation; anterior tracheal-ring hang-up; trauma from forceful delivery; tube displacement during stylet removal.
Corrective manoeuvres: Withdraw and rotate rather than forcing the tube; release anterior-ring impingement; progressively withdraw the stylet while stabilising the tube.
Relevant performance errors: Translation rather than rotation · anterior tracheal-ring hang-up · glottic trauma · tube dislodgement during stylet removal
7. Confirm passage before withdrawing the laryngoscope
Successful device entry into the glottis is not the end of the visual procedure. Maintain the laryngoscopic view until tube passage is confirmed and the tube remains stable during bougie or stylet removal.
Goal: Maintain visual control until tracheal tube placement through the glottis is secure.
Look for: Tube passing between the vocal folds; cuff passing beyond the cords where visible; stable tube position during bougie or stylet removal.
Common problems: Camera withdrawn as soon as the bougie enters the trachea; tube passage not visualised; tube displaced during stylet removal.
Corrective manoeuvres: Maintain the laryngoscope position and camera view until the tube is securely through the glottis.
Relevant performance errors: Premature camera withdrawal · dislodged tube during stylet removal · premature cuff inflation
References
Workshops and courses
- Nelson B. Advanced Airway Management. Medmastery course
Video laryngoscopy library
- Airway Glossary
- Stepwise Approach to Video Laryngoscopy
- Performance Errors in Video Laryngoscopy
- How to Review a Laryngoscopy Video
- Laryngoscopic Airway Anatomy
- Airway Video Cases
FOAMed
- Long N. Adult Intubation Checklist. LITFL
- Long N. Paediatric Intubation Checklist. LITFL
- Weingart S. EMCrit 176 – Updated EMCrit Rapid Sequence Intubation Checklist
- Weingart S. EMCrit 300 – Airway Continuous Quality Improvement and the Resus Airway Bundle
- Weingart S. EMCrit 360 – A Taxonomy of Key Performance Errors for Emergency Intubation (Primer)
Journal articles
- Weingart SD, Barnicle RN, Janke A, Bhagwan SD, Tanzi M, McKenna PJ, Bracey A; Resuscitationists Research Group. A taxonomy of key performance errors for emergency intubation. Am J Emerg Med. 2023 Nov;73:137-144.
- Bryan A, Feltes J, Sweetser PW, Winsten S, Hunter I, Yamane D. Hyperangulated video laryngoscopy in the emergency department: An analysis of errors and factors leading to prolonged apnea time. Am J Emerg Med. 2025 Sep;95:153-158.
- Weingart SD et al. The Airway Lead and the Creation of a Comprehensive Emergency Airway Quality Program. J Emerg Med. 2025 May;72:104-111.
- Bracey A, Lacy AJ, Weingart SD, Ata A, Giuliano AS, Lewis JC, Mantas J, Bayly B, Doyle M, Barnicle RN. A taxonomy of key performance errors associated with hyperangulated video laryngoscopy for emergency intubation. Am J Emerg Med. 2026 Mar;101:152-158.

Dr. Tim Friedmann, MD is an Assistant Professor in the Department of Emergency Medicine at the Icahn School of Medicine at Mount Sinai. He is an Assistant Program Director for the residency program and works clinically at Mount Sinai Hospital and Elmhurst Hospital | Sinai EM |

BA MA (Oxon) MBChB (Edin) FACEM FFSEM. Emergency physician, Sir Charles Gairdner Hospital. Passion for rugby, medical history, medical education, and asynchronous learning #FOAMed evangelist. Co-founder and CTO of Life in the Fast lane | On Call: Principles and Protocols 4e| Eponyms | Books | Horology